

HIPEC Cancer Surgery and Treatment for Ethiopians in India
Five gates every peritoneal-spread case should pass before booking a flight — and why, for a procedure that no published programme in Ethiopia or East Africa currently offers at all, India's dedicated peritoneal- malignancy centres are not simply the best option but, for most patients who genuinely qualify, the only real one.
Cytoreductive surgery with hyperthermic intraperitoneal chemotherapy — CRS-HIPEC — is the treatment that changed peritoneal cancer spread from an automatic terminal diagnosis into, for selected patients, a genuinely treatable disease. In 24 years of arranging surgical care in India for patients across Africa and Asia, this is the procedure where travelling is least about preference and most about arithmetic: the equipment, intensive care infrastructure, and specialist team it demands simply do not exist yet in Ethiopia, and barely exist across East Africa at all. That absence is not unusual by regional standards — it is the norm. Even North Africa, the best-resourced part of the continent for this surgical oncology, offers CRS-HIPEC at only around a quarter of surveyed cancer institutions. India, by contrast, has built dedicated peritoneal malignancy programmes at a number of comprehensive cancer centres, with surgical oncologists who perform this operation as a defined subspecialty, heated-perfusion equipment on standing readiness, and the ICU capacity a fourteen-hour operation genuinely requires. For an Ethiopian patient with peritoneal spread from colorectal, ovarian, appendiceal, or gastric cancer, India is where this treatment actually exists to be delivered well. These five gates walk through whether CRS-HIPEC genuinely fits a specific case, since honest patient selection matters enormously here — and, for the patients it fits, why India is where it is performed most often, most safely, and at a fraction of the cost of comparable centres in the Gulf, Europe, or the United States.
Healing Journeys of Ethiopian Patients






Key Takeaways
- Ethiopian patients with cancer that has spread to the peritoneum may be considered for CRS-HIPEC in carefully selected cases.
- The original cancer matters because colorectal, ovarian, appendiceal and gastric cancers can have different expected outcomes with CRS-HIPEC.
- The Peritoneal Cancer Index (PCI), scored from 0 to 39, helps assess the extent of peritoneal disease and the possibility of complete cytoreduction.
- CRS-HIPEC requires specialised surgical, heated-perfusion, pathology and intensive-care infrastructure.
- The PDF states that no published CRS-HIPEC programme currently operates in Ethiopia or East Africa, making India an important treatment option for suitable patients.
- Patients should review their CT/MRI imaging, pathology and PCI assessment and ask about the centre's CRS-HIPEC experience and complete cytoreduction rates before travelling.
Quick Facts
- Treatment
- CRS-HIPEC Cancer Surgery
- Country
- India
- Patients
- Ethiopian Patients
- Primary Condition
- Peritoneal Cancer Spread
- Main Procedure
- Cytoreductive Surgery with Hyperthermic Intraperitoneal Chemotherapy
- Cancer Origins
- Colorectal, Ovarian, Appendiceal and Gastric
- Key Assessment
- Peritoneal Cancer Index (PCI)
- PCI Range
- 0–39
- Main Surgical Goal
- Complete or Near-Complete Cytoreduction
- Staging Procedure
- CT/MRI and Diagnostic Laparoscopy
- Key Surgical Assessment
- Cancer Resectability
- Main Treatment
- Cytoreductive Surgery and Heated Intraperitoneal Chemotherapy
- Additional Treatment
- Systemic Chemotherapy Before or After Surgery
- Key Specialists
- Surgical Oncologist, Medical Oncologist, Pathologist and ICU Team
- Important Selection Factor
- Cancer Origin, PCI and Complete Cytoreduction Potential
- Why Consider India
- Dedicated Peritoneal Malignancy Programmes and High-Volume CRS-HIPEC Teams
- HIPEC Availability in Ethiopia
- No Published CRS-HIPEC Programme
- Indicative CRS-HIPEC Cost
- USD 8,000–20,000
- Diagnostic Workup Cost
- USD 700–1,600
- Diagnostic Laparoscopy Cost
- USD 1,200–2,200
- Treatment Duration
- Total trip may take approximately 3–5 weeks
- Hospital Stay
- Includes ICU care; duration varies by recovery
- Payment Advice
- Obtain a Written, Itemised Quotation
In Brief
CRS-HIPEC combines cytoreductive surgery, which removes visible peritoneal tumour, with heated intraperitoneal chemotherapy to treat microscopic disease. Suitability depends on the cancer of origin, extent of peritoneal spread and whether complete or near-complete cytoreduction can be achieved. The Peritoneal Cancer Index helps assess disease burden, while diagnostic laparoscopy may help determine resectability. Ethiopian patients considering treatment in India should obtain their imaging and pathology reports and choose a high-volume peritoneal malignancy team with appropriate surgical and ICU infrastructure.
1 Gate One
The end of the road, or a different fight?
A scan or an operation note describing tumour deposits scattered across the peritoneum — the lining of the abdominal cavity — is what usually starts this conversation, and it is often delivered as if it closes every option down to palliative chemotherapy alone. That used to be accurate. It no longer automatically is.
Cytoreductive surgery physically removes visible tumour deposits from the peritoneal surfaces, and HIPEC follows immediately, bathing the abdominal cavity in heated chemotherapy to kill microscopic disease left behind. For carefully selected patients — selection is the entire point of this guide — this combination has moved peritoneal spread from a uniformly terminal finding to a condition some patients are treated through, and some are cured of. Confirm early which category your imaging and pathology point to, since the two conversations that follow are entirely different ones.
2 Gate Two
Which cancer started this?
Peritoneal spread is not one disease with one prognosis. Where the original tumour arose changes the expected benefit of CRS-HIPEC by an order of magnitude, and this should be the first question answered before any operation is discussed.
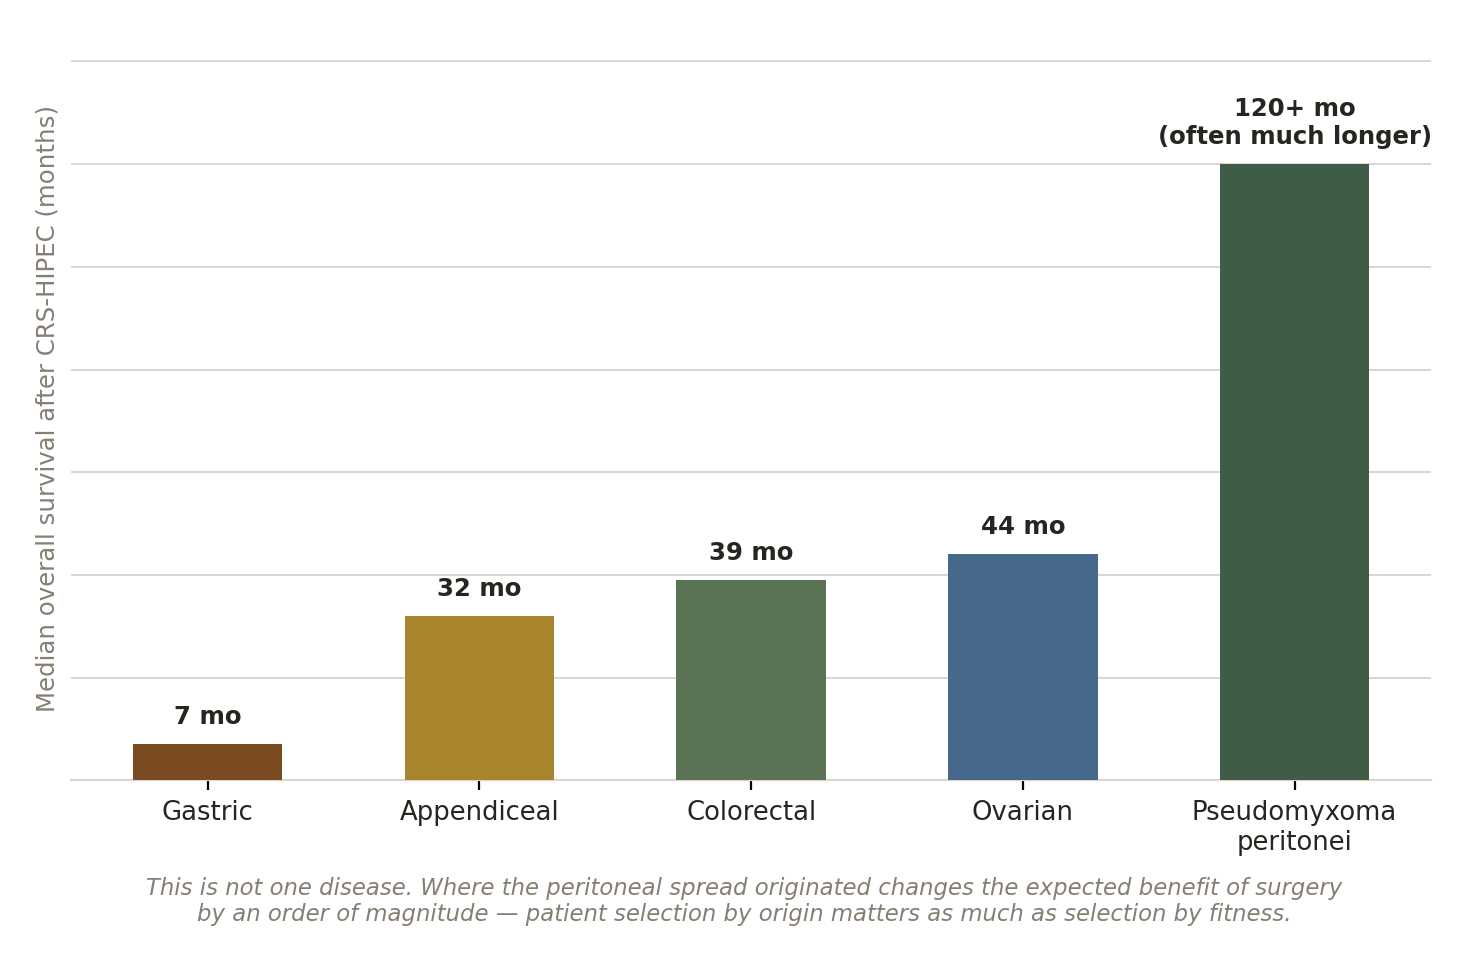
Selection by cancer of origin is as important as selection by fitness for surgery.
Why Ethiopian patients reach this gate more often than most: published Ethiopian data shows roughly six in ten ovarian cancers and a similar share of gastric cancers are diagnosed at an advanced stage, well past routine screening catching them early. Peritoneal spread from these cancers is a genuine, recurring presentation in Ethiopian oncology, not a rare edge case — which is exactly why a real referral pathway to CRS-HIPEC matters.
Pseudomyxoma peritonei, arising from the appendix, behaves the most favourably of all and can achieve exceptional long-term survival even with extensive disease. Gastric-origin spread behaves the least favourably, and for some gastric presentations, an honest specialist will advise against CRS-HIPEC even where the patient is otherwise fit. Ask explicitly which category applies before travelling.
3 Gate Three
Can it be cleared completely?
The single strongest predictor of whether CRS-HIPEC helps is not the operation itself but whether it achieves complete, or near-complete, cytoreduction — removing all or nearly all visible tumour. Surgeons score this with the Peritoneal Cancer Index (PCI), a 0-to-39 scale of how far disease has spread across thirteen abdominal regions, assessed at diagnostic laparoscopy or at the start of surgery itself.
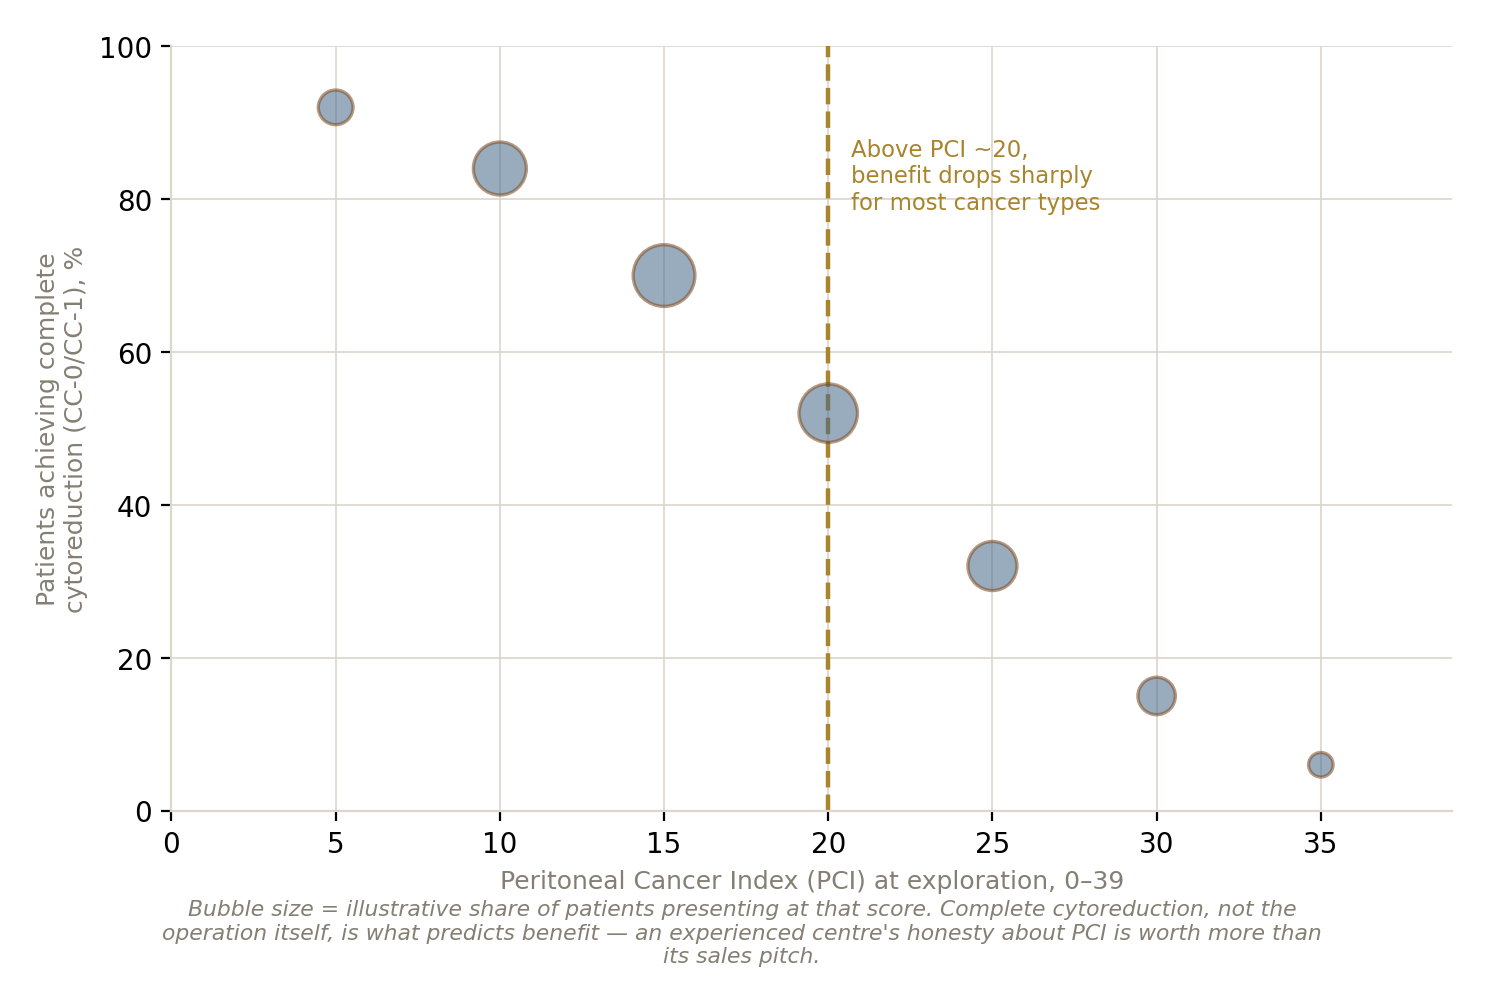
Above a PCI of roughly 20, the odds of a genuinely complete operation fall sharply for most cancer types.
This is where an experienced, high-volume CRS-HIPEC programme earns its reputation honestly: by saying, before surgery, that a PCI is too high to help rather than operating anyway. India's dedicated peritoneal malignancy units see enough volume to make this judgment reliably, with diagnostic laparoscopy used specifically to confirm resectability before committing to the full procedure. Ask any centre what their complete cytoreduction (CC-0/CC- 1) rate is, and what share of patients they turn away after laparoscopic staging — a centre with nothing to say to that second question is not one to trust with the first.
4 Gate Four
Could this be done in Ethiopia?
Honestly: not yet, and not close. CRS-HIPEC requires a dedicated heated-perfusion circuit, a surgical oncology team trained specifically in peritonectomy technique, intraoperative frozen-section pathology, and an intensive care unit equipped for a patient who may be in theatre for up to fourteen hours. No published programme currently offers this combination anywhere in Ethiopia or East Africa, and even the continent's better-resourced regions manage it at only a minority of centres.
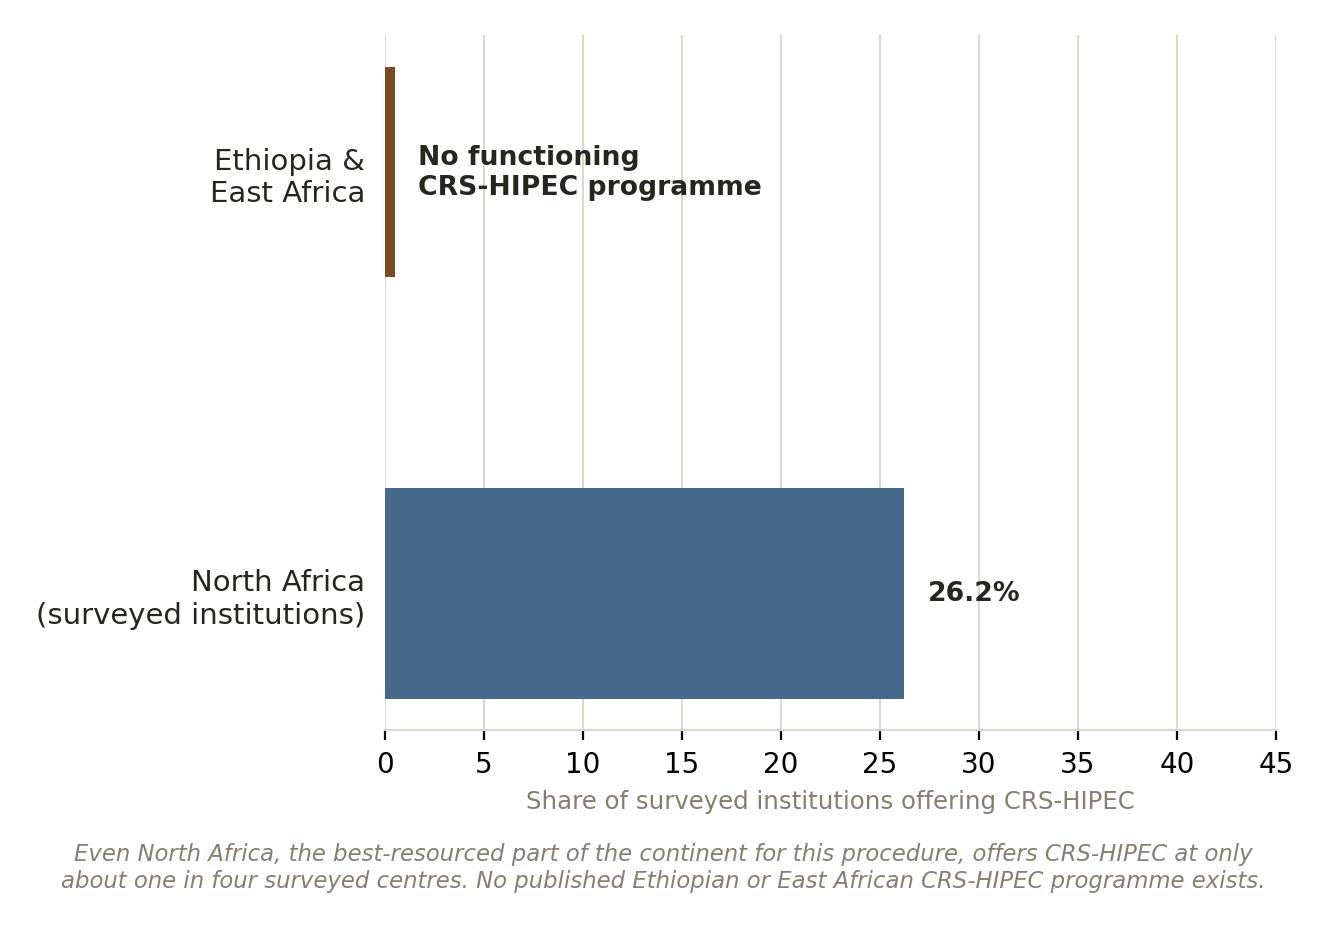
This is not a capacity gap to work around. It is an absence to travel past.
This is precisely why India's position in this field matters so directly. Leading Indian cancer centres have run dedicated peritoneal surface malignancy programmes for over a decade, with surgical oncologists who perform CRS-HIPEC as a high-volume subspecialty rather than an occasional complex case, on-site heated-perfusion equipment, and ICU teams experienced in this surgery's specific post-operative physiology. For a disease where outcome depends this heavily on technical execution and honest patient selection, that concentration of experience is not a convenience — for an Ethiopian patient today, it is close to the only route to this treatment existing at all.
A second opinion on the imaging, pathology, and PCI staging before committing to a specific centre is worth arranging. Ask how many CRS-HIPEC cases the surgical team performs each year, and by which cancer of origin — India's high-volume peritoneal malignancy units answer this with real numbers.
5 Gate Five
Is the money arranged?
Ethiopia's health financing does not follow a patient abroad. Community-Based Health Insurance covers contracted facilities inside the country, and the formal-sector scheme still isn't settling claims. Since February 2026 a bank may release up to US$20,000 per case against a letter from the treating hospital, without a visa or ticket in hand.
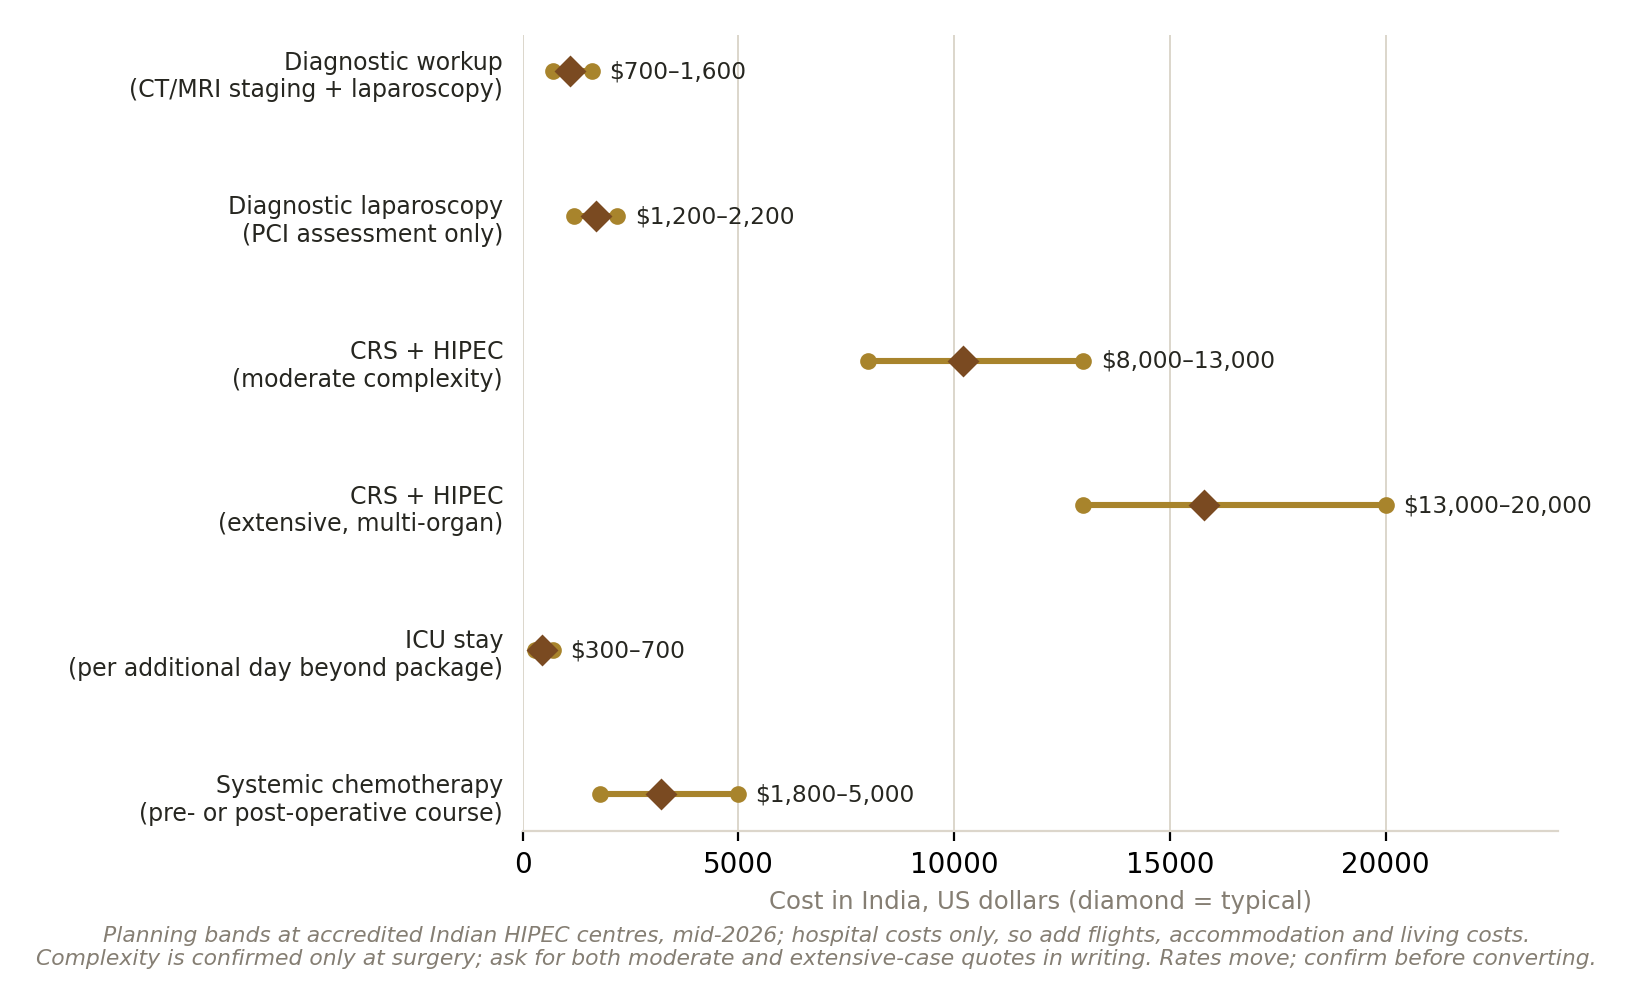
Budget for the complexity your PCI actually points to, not the most familiar figure.
The figures differ substantially by extent of disease: a moderate-complexity case sits well below an extensive, multi- organ resection. Even at the top of these ranges, treatment at a leading Indian peritoneal malignancy centre remains a fraction of an equivalent package in the Gulf, Europe, or the United States, where this procedure is often priced several times higher for materially the same technique. Confirm the expected complexity, based on your PCI staging, before assuming any single number applies to your case.
| A quotation, annotatedA composite of the HIPEC quotes that reach me, with the questions I send back. | |
| CRS + HIPEC — USD 12,000 | Moderate or extensive complexity? Ask what determines the band. |
| Includes: diagnostic laparoscopy | Good sign. Ask what you owe if PCI is found too high to proceed. |
| Includes: 10 days admission incl. ICU | Ask what a longer ICU stay or a complication would add. |
| Pathology: intraoperative frozen section | Confirm this is genuinely real-time, not sent out and delayed. |
| Excludes: pre/post-operative systemic chemotherapy | Ask if your cancer of origin typically needs this, and its cost. |
| Excludes: stoma care if required | Ask whether your cytoreduction is likely to need a temporary stoma. |
In 24 years the CRS-HIPEC patients most satisfied with their outcome chose a genuinely high-volume peritoneal malignancy programme, asked for honest PCI and CC-rate numbers before the price, and travelled with realistic expectations about what their cancer of origin could achieve.
The Ethiopian practicalities
Ethiopian Airlines flies non-stop from Bole to Delhi, Mumbai, Bengaluru, Chennai, and Hyderabad. Ask for written clearance to fly rather than assuming a fixed number of days after surgery, since recovery from CRS-HIPEC is longer and more variable than most abdominal operations. Yellow fever certification is required at least ten days before arrival, oral polio vaccination roughly four weeks before. The medical visa follows the hospital's invitation letter through the Embassy of India, Addis Ababa, and an attendant is worth arranging for the full hospital stay. Where treatment spans the Orthodox fasting calendar, raise this with the hospital's dietary team beforehand, since post-operative nutrition needs are demanding after this procedure. Confirm current rules with the Embassy, since they change, and ask for an Amharic-speaking coordinator to carry a written plan back to a named oncologist in Ethiopia.
Straight Answers for Ethiopian Patients about HIPEC Cancer Surgery and Treatment in India
My doctor said the cancer has spread to the peritoneum. Is this the end of treatment?
Not automatically. Peritoneal spread was once treated as terminal, but for selected patients, CRS-HIPEC can extend survival substantially, and occasionally offer long-term remission. Selection depends heavily on the cancer of origin and how completely the tumour can be removed.
Is HIPEC available in Ethiopia?
No published programme currently operates in Ethiopia or East Africa. Even North Africa, the best-resourced part of the continent for this procedure, offers it at only about a quarter of surveyed centres. It requires dedicated equipment, ICU capacity, and a team performing it regularly.
What is the Peritoneal Cancer Index and why does it matter?
It scores how extensively tumour has spread across the abdominal cavity, from 0 to 39, and is one of the strongest predictors of whether complete cytoreduction is achievable. A high score doesn't automatically rule out surgery, but should prompt an honest conversation about expected benefit.
How long does treatment in India take?
The operation itself typically runs eight to fourteen hours, followed by several ICU days and one to two weeks of further recovery. Staging beforehand and any chemotherapy around the operation can extend the total trip to three to five weeks.
Who pays for this in Ethiopia?
You do. Neither Community-Based Health Insurance nor the pending formal-sector scheme funds treatment abroad, though a bank may now advance up to US$20,000 against the treating hospital's letter.
A closing word
Send the CT or MRI imaging, any operative or laparoscopy notes, and the pathology confirming where the cancer started. I will tell you honestly whether CRS-HIPEC is likely to help, and for patients it genuinely fits, why India's peritoneal malignancy programmes are, for now, close to the only place this treatment exists to be delivered at all.
Sources
- 🌐 Current opinion and practice on peritoneal carcinomatosis management: the North African perspective. Front Oncol / PMC. 2022
- 🌐 Initial experience of cytoreductive surgery (CRS) and hyperthermic intraperitoneal chemotherapy (HIPEC) in a Baltic country center
- 🌐 Diagnosis and risk factors of advanced cancers in Ethiopia. J Cancer Prev. 2019
- 🌐 National Medical Commission of India — Indian Medical Register
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH), Quality Council of India
- 🌐 National Bank of Ethiopia Directive FXD/04/2026 (foreign exchange, advance payments for treatment abroad); Embassy of India, Addis Ababa
Frequently Asked Questions by Ethiopians about HIPEC Cancer Surgery and Treatment in India
What is HIPEC cancer treatment?
HIPEC is heated chemotherapy delivered directly into the abdominal cavity after cytoreductive surgery. The surgery removes visible tumour while HIPEC aims to treat microscopic cancer cells remaining in the abdomen.
Which cancers can be treated with CRS-HIPEC?
The PDF discusses peritoneal spread originating from colorectal, ovarian, appendiceal and gastric cancers, as well as pseudomyxoma peritonei. Suitability varies according to the cancer's origin and extent.
Is every patient with peritoneal cancer suitable for HIPEC?
No. Patient selection is critical. The cancer's origin, overall fitness, extent of disease and possibility of complete or near-complete cytoreduction influence suitability.
What is the Peritoneal Cancer Index?
The Peritoneal Cancer Index, or PCI, measures the extent of tumour spread across the abdominal cavity on a scale of 0 to 39. A higher PCI can make complete tumour removal more difficult.
Why is diagnostic laparoscopy important before CRS-HIPEC?
Diagnostic laparoscopy can help assess the actual extent of peritoneal disease and determine whether complete cytoreduction is realistically achievable before proceeding with major surgery.
Is HIPEC available in Ethiopia?
The PDF states that no published CRS-HIPEC programme currently operates in Ethiopia or East Africa. India is therefore highlighted as an important option for Ethiopian patients who are appropriate candidates.
How much does CRS-HIPEC cost in India?
The PDF gives an indicative range of approximately USD 8,000–13,000 for moderate-complexity CRS-HIPEC and USD 13,000–20,000 for extensive multi-organ cases. Additional diagnostic and chemotherapy costs may apply.
How long does HIPEC treatment in India take?
The operation itself may take approximately 8–14 hours, followed by ICU care and recovery. Including staging and chemotherapy around surgery, the total trip may extend to approximately three to five weeks.
What should Ethiopian patients ask a HIPEC centre before choosing treatment?
Patients should ask about annual CRS-HIPEC case volume, experience by cancer type, complete cytoreduction rates and how often patients are declined after staging. These factors can help assess the centre's experience and patient-selection approach.
What should Ethiopian patients carry when travelling for HIPEC treatment?
Patients should carry CT or MRI imaging, pathology reports and operative or laparoscopy notes where available. They should also obtain a written treatment plan and itemised quotation before travelling.
Page Summary
This guide explains CRS-HIPEC for Ethiopian patients with selected cancers that have spread to the peritoneum. It covers cancer of origin, PCI staging, cytoreductive surgery, HIPEC and patient selection. It also explains treatment costs, recovery, travel preparation and why Indian peritoneal malignancy centres specialised may be considered for eligible patients.
Citation Block
| Topic | Information |
|---|---|
| Topic Information | HIPEC Cancer Surgery and Treatment for Ethiopians in India |
| Treatment | CRS-HIPEC |
| Country | India |
| Intended Audience | Ethiopian Patients |
| Primary Condition | Peritoneal Cancer Spread |
| Main Procedure | Cytoreductive Surgery with HIPEC |
| Cancer Origins | Colorectal, Ovarian, Appendiceal and Gastric |
| Key Assessment | Peritoneal Cancer Index |
| PCI Range | 0–39 |
| Surgical Goal | Complete or Near-Complete Cytoreduction |
| Staging | CT/MRI and Diagnostic Laparoscopy |
| Resectability Assessment | Diagnostic Laparoscopy Where Appropriate |
| Additional Treatment | Systemic Chemotherapy |
| Key Specialists | Surgical Oncologist, Medical Oncologist, Pathologist and ICU Team |
| Selection Factors | Cancer Origin, PCI and Cytoreduction Potential |
| HIPEC Availability | No Published Programme in Ethiopia or East Africa |
| Why Consider India | Dedicated Peritoneal Malignancy Programmes |
| CRS-HIPEC Cost | USD 8,000–20,000 |
| Diagnostic Workup | USD 700–1,600 |
| Diagnostic Laparoscopy | USD 1,200–2,200 |
| Treatment Duration | Approximately 3–5 Weeks |
| Follow-Up | Continued Oncology Care |
| Author | Dr. Dheeraj Bojwani |
| Experience | 24+ Years |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Ethiopia










Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Ethiopia who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Eritrea
- Djibouti
- Somalia
- Kenya
- Sudan
- Burundi
- Comoros
- Ethiopia
- Madagascar
- Malawi
- Mauritius
- Mozambique
- Rwanda
- South Sudan
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Ethiopia to India: Your Complete Patient Support Guide
- Brain Tumour Surgery in India for Ethiopians
- Cancer Treatment in India for Ethiopians
- Cardiac Surgery in India for Ethiopian Patients
- Cervical and Disc Replacement Surgery in India for Ethiopians
- Cosmetic and Plastic Surgery in India for Ethiopians
- CyberKnife Treatment in India for Ethiopians
- Eye Surgery in India for Ethiopians
- Gamma Knife Treatment in India for Ethiopians
- Heart Valve Replacement Surgery in India for Ethiopians
- Hip Surgery in India for Ethiopian Patients
- Knee Surgery in India for Ethiopian Patients
- Laparoscopic and Robotic Myomectomy Surgery in India for Ethiopians
- Neurosurgery in India for Ethiopians
- Paediatric Cardiac Surgery in India for Ethiopians
- Paediatric Neurosurgery in India for Ethiopians
- Prostate Cancer Treatment and Surgery in India for Ethiopians
- Robotic Cancer Surgery in India for Ethiopians
- Scoliosis Surgery in India for Ethiopians