

Choosing the Best Prostate Cancer Treatment and Surgery Surgeon and Hospital in India: A Guide for Ethiopian Patients
For many men, the first and most important prostate cancer decision isn't which surgeon to choose — it's whether surgery is needed right now at all. For those who do need it, how well nerve-sparing technique is performed determines not just whether the cancer is cured, but whether continence and sexual function are preserved afterward.
Most patients researching prostate cancer surgery in India spend the bulk of their time comparing prices, and understandably so — cost is often what makes the trip possible at all. But price is the easiest variable to compare and, on its own, the least useful one for predicting how the treatment actually turns out, both in terms of cancer control and quality of life afterward. Two quotes that look identical on paper can represent very different surgeons, very different hospitals, and, for this cancer specifically, very different outcomes for continence and sexual function. This matters more for prostate cancer than for many other cancers, because of two things that deserve honest attention before any surgeon or hospital is chosen. The first is that surgery is not automatically the right first step: for many men with low-risk, localised disease, active surveillance, regular monitoring without immediate treatment, is a legitimate, guideline-supported alternative, and overtreatment of low-risk prostate cancer is a well-documented concern worldwide. The second is that, for those who genuinely do need surgery, the outcome that matters isn't only cancer control but whether nerve-sparing technique preserves urinary continence and erectile function, a surgical skill that varies meaningfully with a surgeon's specific experience and shapes quality of life for years afterward. In 24 years of arranging surgical care in India for patients across Africa and Asia, these two honest conversations, whether treatment is needed now, and how well function can genuinely be preserved, are what separate a well-managed case from a regretted one. The two decisions, surgeon and hospital, deserve equal weight. A skilled surgeon without the right hospital infrastructure behind them, and a well-equipped hospital without a genuinely experienced surgeon, can each independently produce a disappointing result. What follows is a practical guide to evaluating both, together with the other factors that quietly shape how well the entire journey goes, and how well function is preserved once it's over.
Healing Journeys of Ethiopian Patients






Key Takeaways
- The guide explains that the first prostate cancer decision is not always whether to have surgery. For many men with low-risk, localised disease, active surveillance may be a legitimate option based on factors such as Gleason score, PSA trend and imaging. The guide therefore recommends discussing the complete treatment pathway before committing to an operation.
- The page 2 graphic gives equal 50% weighting to the surgeon and hospital. Surgeon assessment focuses on NMC registration, recognised urology or surgical oncology qualifications with uro-oncology training, radical prostatectomy experience and, specifically, annual nerve-sparing prostatectomy volume.
- The page 3 chart illustrates an increasing pattern in illustrative 12-month continence preservation with higher annual nerve-sparing prostatectomy volume, from 58% for fewer than 10 cases annually to 92% for 100+ cases. The guide therefore recommends asking about the surgeon's specific nerve-sparing experience and tracked continence and potency outcomes.
- The guide stresses that nerve-sparing should not simply be a default claim. Patients should ask what proportion of the surgeon's cases are nerve-sparing and request information about continence and erectile-function preservation, while also discussing whether robotic-assisted, laparoscopic or open surgery is most appropriate for their individual case.
- Hospital assessment focuses on NABH or JCI accreditation, robotic-assisted technology, dedicated uro-oncology volume and a multidisciplinary tumour board that includes radiation oncology. The page 5 chart shows an illustrative major complication pattern of 11.4% without formal accreditation, 5.6% with NABH and 3.4% with JCI.
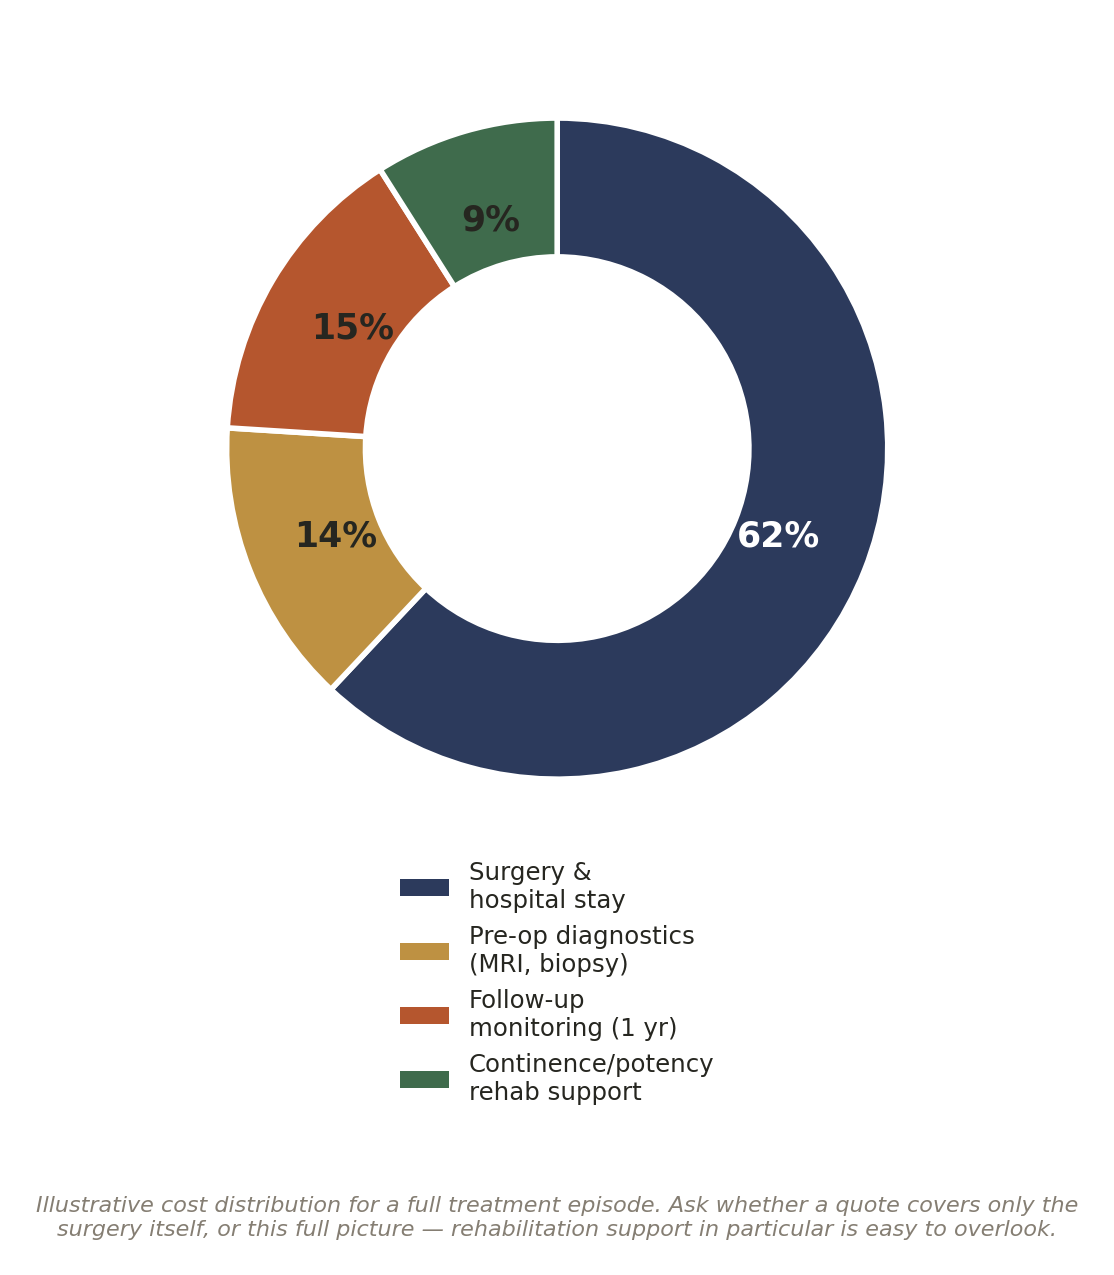
- The guide recommends a genuine second opinion, independent credential verification and full cost transparency across the entire treatment journey. The page 8 graphic illustrates an indicative cost distribution of 62% for surgery and hospital stay, 14% for pre-operative diagnostics, 15% for one-year follow-up monitoring and 9% for continence/potency rehabilitation support.
- For Ethiopian patients, the guide emphasises long-term PSA surveillance and functional rehabilitation after returning home. A written plan should identify how PSA monitoring, continence recovery and potency rehabilitation will continue, with a named urologist in Ethiopia and a clear post-discharge contact.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
- Treatment
- Prostate Cancer Treatment & Surgery
- Patients
- Ethiopian Patients
- Key Specialist
- Uro-Oncologist / Prostate Cancer Surgeon
- Selection Weighting
- 50% surgeon / 50% hospital
- Key Principle
- Confirm whether surgery is actually appropriate
- Qualification Check
- MCh Urology or equivalent recognised degree with uro-oncology training
- Treatment Options
- Active surveillance, surgery and radiation-based treatment
- Volume Check
- Annual radical prostatectomy and nerve-sparing cases
- Outcome Check
- 12-month continence and potency preservation
- Surgical Approaches
- Robotic-assisted, laparoscopic or open surgery
- Hospital Check
- NABH or JCI accreditation
- Technology
- Robotic-assisted surgical platform
- Cancer Care
- Dedicated uro-oncology programme
- Multidisciplinary Review
- Tumour board including radiation oncology
- Rehabilitation
- Structured pelvic-floor and functional rehabilitation
- Second Opinion
- Pathology, imaging and staging
- Cost Check
- Diagnostics, surgery, hospital stay and rehabilitation
- Follow-Up
- PSA and functional monitoring in Ethiopia
- Key Warning
- Do not choose surgery or a surgeon based only on price or robotic technology
- Decision Principle
- Choose the treatment pathway and specialist that best balance cancer control with long-term quality of life.
In Brief
For Ethiopian patients considering prostate cancer treatment in India, the guide recommends prioritising appropriate treatment selection, condition-specific uro-oncology expertise, nerve-sparing experience, multidisciplinary review and structured rehabilitation rather than choosing based on price alone. A second opinion, complete cost estimate and long-term PSA and functional follow-up plan should be confirmed before travelling.
01 The Prostate Cancer Surgeon in India: What Actually Matters
A surgeon's qualifications are the starting point, not the finish line. The following, taken together, give a genuinely reliable picture.
Registration and formal qualification. Confirm the surgeon is registered with the National Medical Commission of India (NMC), and holds a postgraduate qualification in urology or surgical oncology with dedicated uro-oncology training (MCh Urology, or an equivalent recognised degree). This is independently verifiable through the NMC's public Indian Medical Register and is worth checking directly rather than taking on trust.
Willingness to discuss active surveillance honestly. Before any surgical plan, ask whether active surveillance was genuinely considered for your specific case, based on your Gleason score, PSA trend, and imaging, not assumed unsuitable by default. A surgeon confident enough to recommend watchful monitoring when it's the better option is showing real trustworthiness.
Case volume, specifically in radical prostatectomy. Ask directly how many prostatectomies, and specifically how many nerve-sparing procedures, the surgeon performs each year. Functional outcomes are strongly linked to a surgeon's specific, ongoing experience with this exact technique.
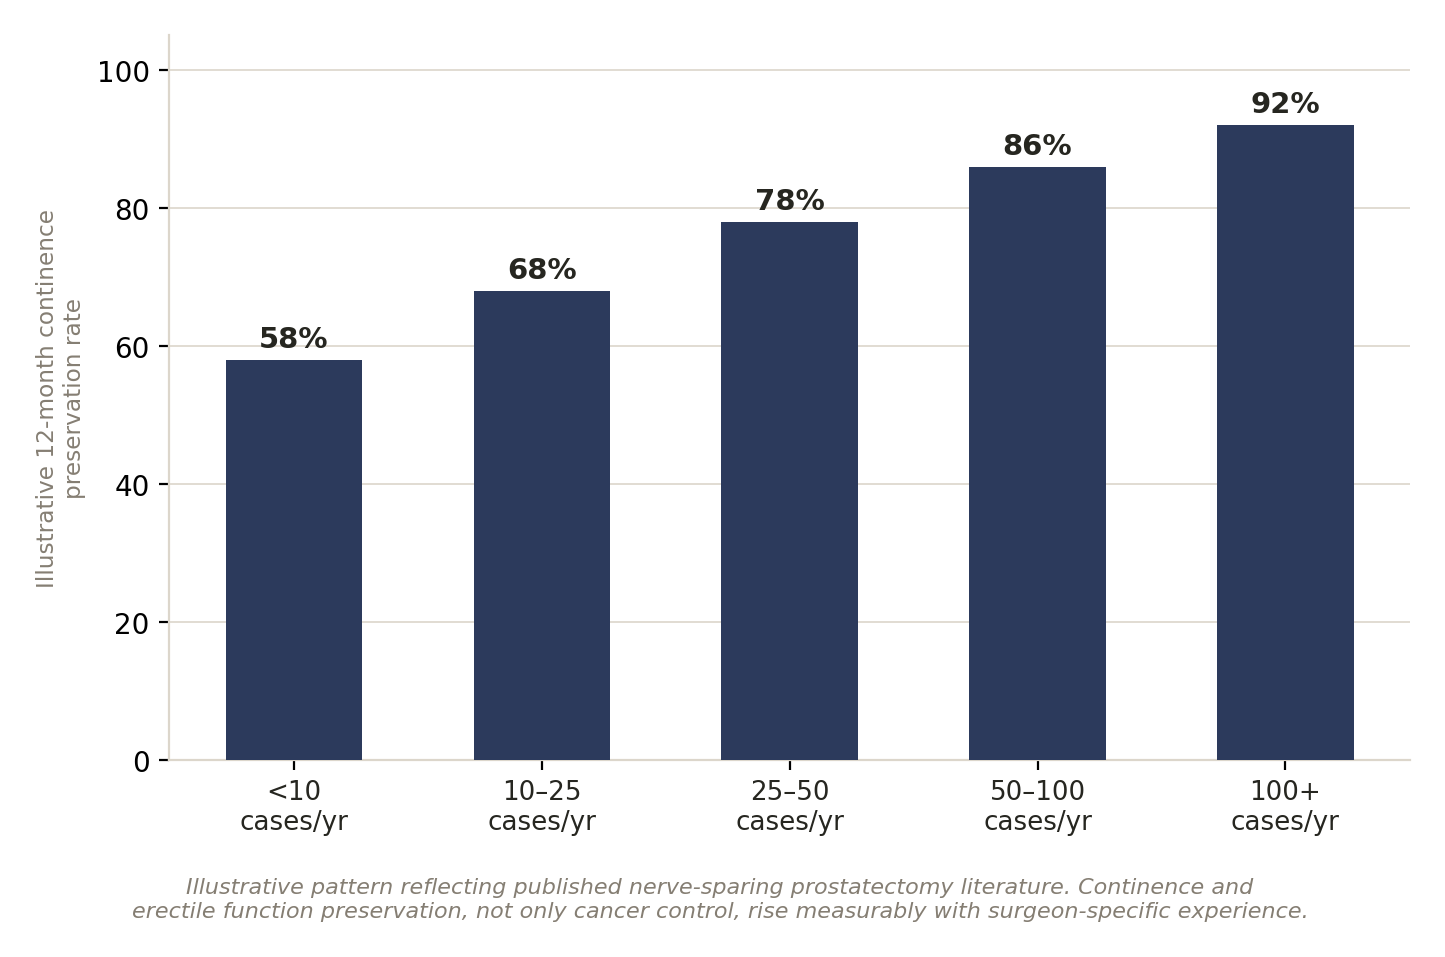
Why "how many nerve-sparing procedures do you do a year?" matters as much as the cancer outcome itself.
Genuine nerve-sparing expertise, not a default claim. Ask specifically what proportion of the surgeon's cases are nerve-sparing, and their own published or tracked continence and potency preservation rates at twelve months, not just cancer clearance rates.
Comfort discussing robotic-assisted, laparoscopic, and open approaches. Ask which technique is recommended for your specific case and why, rather than the surgeon defaulting to whichever approach they are most comfortable performing regardless of fit. Each approach carries different trade-offs in recovery time, blood loss, and precision near the nerve bundles.
Transparency about outcomes and experience with international patients. A surgeon willing to discuss their own recurrence, continence, and potency outcomes candidly, and who is accustomed to patients travelling from Ethiopia and the wider region, is showing exactly the accountability and practical attentiveness worth trusting.
02 The Prostate Cancer Hospital in India: What Actually Matters
The hospital is not simply a venue for the surgeon's work; its systems, technology, and support services shape both the safety of the operation and the quality of life afterward.
Accreditation. National Accreditation Board for Hospitals & Healthcare Providers (NABH) accreditation is the baseline worth confirming for any hospital under consideration; Joint Commission International (JCI) accreditation, held by a smaller number of leading Indian hospitals, reflects an internationally benchmarked standard of safety and quality worth actively seeking out for a diagnosis this significant.
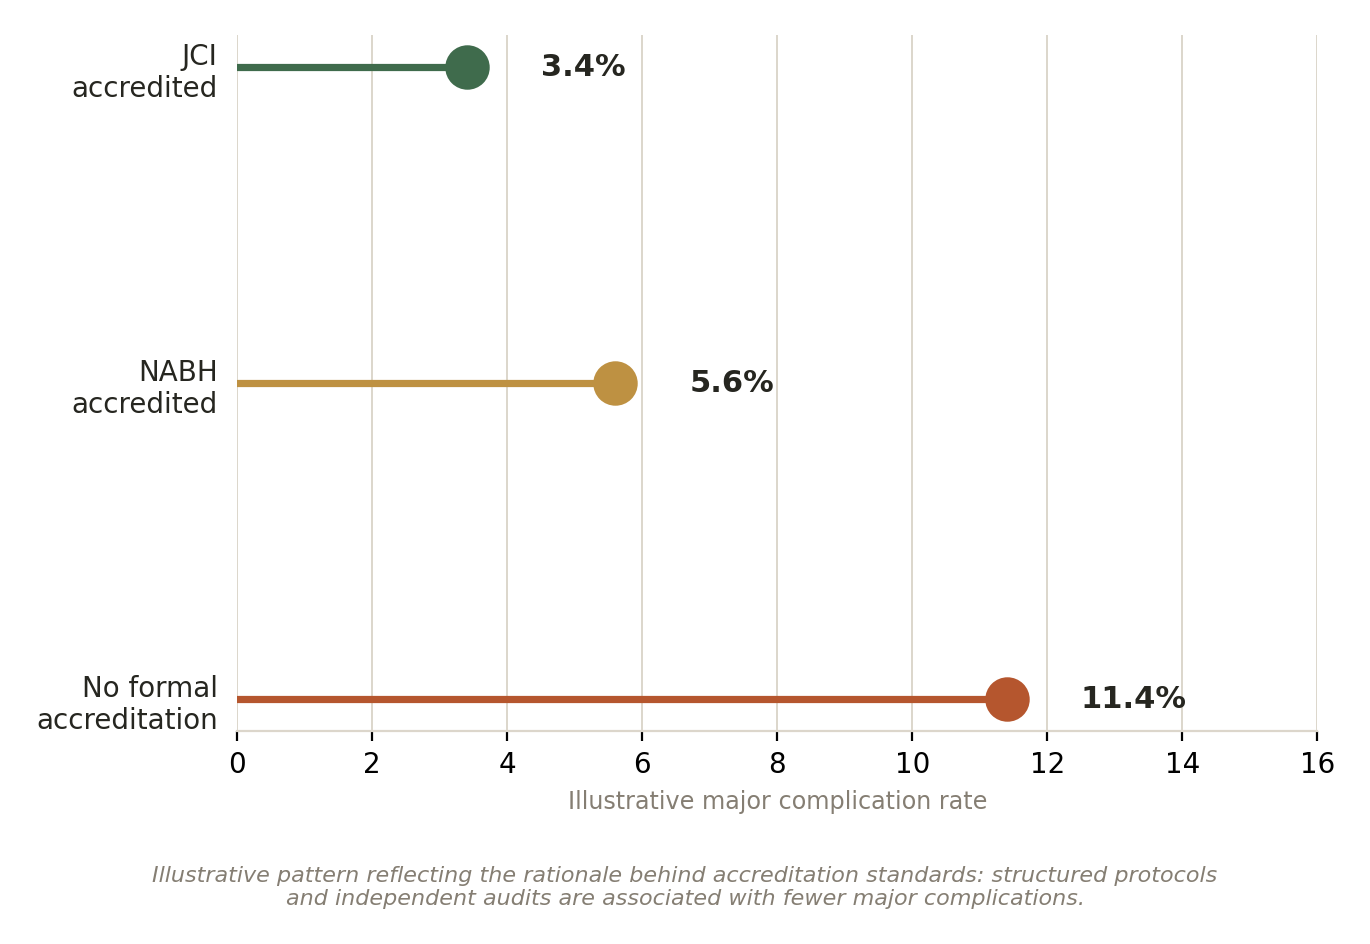
Accreditation is a proxy for structured protocols and independent oversight, not a formality.
Access to robotic-assisted surgical technology. Confirm the hospital has genuine robotic-assisted platforms available, not just laparoscopic or open surgery, so the technique recommendation isn't limited by what the centre happens to have.
Dedicated uro-oncology volume. Hospitals that perform a high annual volume of prostate cancer surgery, ideally through a dedicated urology or uro-oncology programme, tend to have more refined protocols and better functional outcomes than general surgical units for whom this is a smaller part of a broader caseload.
A genuine multidisciplinary tumour board, including radiation oncology. Since radiation is a genuine alternative to surgery for many cases, ask whether your case was reviewed by a team including radiation oncology, not decided by the surgical team alone.
Structured post-operative continence and rehabilitation support. Ask whether the hospital offers a structured pelvic floor rehabilitation programme after surgery, since this materially affects how quickly continence returns, sometimes shortening recovery from many months to a matter of weeks.
International patient services. A dedicated international patient department, offering visa support, airport coordination, interpreter or Amharic-speaking liaison support, and clear pre-departure communication, is a meaningful sign that the hospital is genuinely set up for patients travelling from Ethiopia, not simply willing to accept them.
03 Other Factors in India That Quietly Shape the Outcome of Prostate Cancer Treatment
Beyond the surgeon and the hospital individually, a handful of practical factors determine how smoothly the whole process, and the recovery of function afterward, actually goes.
A genuine second opinion. Before committing to travel, it is worth having a second specialist review the pathology, imaging, and staging to confirm whether surgery, radiation, or active surveillance is genuinely the right path for your specific case.
Independent credential verification. Do not rely solely on a hospital's own marketing material. Cross-check the surgeon's registration on the NMC's Indian Medical Register, and the hospital's accreditation status through the NABH or JCI's own public directories.
Full cost transparency across the whole treatment picture. Ask for a detailed, itemised estimate covering diagnostics, surgery, hospital stay, and follow-up rehabilitation support, not just the operating theatre fee.
Clear communication throughout the journey. Confirm who your point of contact will be before arrival, during the hospital stay, and after discharge, and that this person can communicate clearly with you throughout, not only through a general enquiries line.
A concrete long-term surveillance and rehabilitation plan. Ask specifically how PSA monitoring and continence or potency rehabilitation will continue once you are back in Ethiopia, with a written plan handed to a named urologist in Ethiopia.
Why this balance matters in practice: a brilliant surgeon operating without strong hospital systems and rehabilitation support behind them, and a state-of-the-art hospital without a surgeon genuinely experienced in nerve-sparing technique, can each still produce a disappointing result. The strongest choice is where both are independently verified to be excellent, not one compensating for the other.
A practical checklist before you commit
- Surgeon's NMC registration verified independently
- Active surveillance genuinely discussed as an option
- Surgeon's specific nerve-sparing case volume confirmed
- Hospital's NABH or JCI accreditation verified independently
- Robotic-assisted technology availability confirmed
- Hospital's annual uro-oncology volume confirmed
- Multidisciplinary tumour board including radiation oncology confirmed
- Post-operative continence rehabilitation programme confirmed
- Second opinion obtained on treatment path
- Full itemised cost estimate for the whole journey requested
- Long-term PSA and function follow-up plan confirmed
- Named post-discharge follow-up contact confirmed
A closing word
Send your PSA history, biopsy and Gleason score results, and any imaging. I will help you compare specific surgeons and hospitals against these exact criteria, so the decision rests on verified substance rather than the most polished website or the lowest number on a quote.
Sources
- 🌐 National Medical Commission of India — Indian Medical Register, for verifying a surgeon's qualification and registration
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH), Quality Council of India
- 🌐 Joint Commission International — directory of JCI-accredited organisations worldwide
- 🌐 Active surveillance as a management option for low-risk localised prostate cancer
Frequently Asked Questions by Ethiopians about Prostate Cancer Treatment and Surgery Surgeons and Hospitals in India
Is surgery always necessary for prostate cancer?
No. The guide emphasises that active surveillance may be appropriate for some men with low-risk, localised disease. The decision should consider the Gleason score, PSA trend and imaging.
What qualification should I check for a prostate cancer surgeon?
Confirm that the surgeon is NMC registered and has MCh Urology or an equivalent recognised qualification with dedicated uro-oncology training.
Why is nerve-sparing experience important?
Nerve-sparing technique can affect urinary continence and erectile function after surgery. The guide recommends asking specifically about annual nerve-sparing volume and the surgeon's tracked functional outcomes.
Should I ask about robotic surgery?
Yes, but the guide recommends asking which approach is appropriate for your specific case rather than assuming robotic surgery is automatically superior. Robotic-assisted, laparoscopic and open approaches may have different trade-offs.
What hospital accreditation should I check?
The guide recommends verifying NABH or JCI accreditation, considering accreditation an indicator of structured protocols and independent oversight.
Why should radiation oncology be part of the discussion?
Radiation can be a genuine alternative to surgery for some patients. The guide therefore recommends a multidisciplinary tumour board that includes radiation oncology rather than having the treatment decision made by the surgical team alone.
What rehabilitation should I ask about?
Ask whether the hospital provides a structured pelvic-floor and functional rehabilitation programme, particularly for continence recovery and sexual-function rehabilitation.
Should I get a second opinion?
Yes. The guide recommends having another specialist review the pathology, imaging and staging to confirm whether active surveillance, radiation or surgery is the most appropriate pathway.
What should the cost estimate include?
Request a complete written estimate covering diagnostics, surgery, hospital stay, follow-up monitoring and rehabilitation, rather than comparing only the operating-theatre or surgeon fee.
How should follow-up be managed after returning to Ethiopia?
Before travelling, confirm a written plan for PSA monitoring, continence and potency rehabilitation, with a named urologist in Ethiopia and a clear post-discharge contact.
Page Summary
This guide helps Ethiopian patients evaluate prostate cancer treatment options, surgeons and hospitals in India, giving equal importance to surgeon expertise and hospital systems. The page 3 chart highlights the relationship between nerve-sparing experience and illustrative continence preservation, while the page 5 chart reinforces the importance of accreditation and structured hospital systems. Active surveillance, multidisciplinary review, nerve-sparing expertise, rehabilitation, transparent costs and long-term PSA follow-up are central to the selection process.
Citation Block
| Topic | Information |
|---|---|
| Topic | Choosing the Best Prostate Cancer Treatment and Surgery Surgeon and Hospital in India for Ethiopian Patients |
| Treatment | Prostate Cancer Treatment & Surgery |
| Patients | Ethiopian Patients |
| Key Specialist | Uro-Oncologist / Prostate Cancer Surgeon |
| Selection Weighting | 50% surgeon / 50% hospital |
| Qualification | MCh Urology or equivalent recognised qualification with uro-oncology training |
| Treatment Assessment | Active surveillance, surgery or radiation-based treatment |
| Surgical Volume | Annual radical prostatectomy and nerve-sparing cases |
| Functional Outcomes | Continence and potency preservation at 12 months |
| Surgical Approaches | Robotic-assisted, laparoscopic and open surgery |
| Hospital Accreditation | NABH or JCI |
| Technology | Robotic-assisted surgical platform |
| Uro-Oncology Volume | Dedicated prostate cancer surgery programme |
| Multidisciplinary Care | Tumour board including radiation oncology |
| Rehabilitation | Structured post-operative continence and functional support |
| Second Opinion | Pathology, imaging, staging and treatment pathway |
| Cost Assessment | Diagnostics, surgery, hospital stay, monitoring and rehabilitation |
| International Support | Visa, airport and Amharic-speaking liaison services |
| Follow-Up | PSA monitoring and functional rehabilitation in Ethiopia |
| Warning Signs | Surgery assumed without discussing alternatives or unclear functional outcomes |
| Key Decision | Verify the treatment pathway, nerve-sparing expertise and hospital systems together |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Ethiopia










Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Ethiopia who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Eritrea
- Djibouti
- Somalia
- Kenya
- Sudan
- Burundi
- Comoros
- Ethiopia
- Madagascar
- Malawi
- Mauritius
- Mozambique
- Rwanda
- South Sudan
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Ethiopia to India: Your Complete Patient Support Guide
- Brain Tumour Surgery in India for Ethiopians
- Cancer Treatment in India for Ethiopians
- Cardiac Surgery in India for Ethiopian Patients
- Cervical and Disc Replacement Surgery in India for Ethiopians
- Cosmetic and Plastic Surgery in India for Ethiopians
- CyberKnife Treatment in India for Ethiopians
- Eye Surgery in India for Ethiopians
- Gamma Knife Treatment in India for Ethiopians
- Heart Valve Replacement Surgery in India for Ethiopians
- Hip Surgery in India for Ethiopian Patients
- Knee Surgery in India for Ethiopian Patients
- Laparoscopic and Robotic Myomectomy Surgery in India for Ethiopians
- Neurosurgery in India for Ethiopians
- Paediatric Cardiac Surgery in India for Ethiopians
- Paediatric Neurosurgery in India for Ethiopians
- Prostate Cancer Treatment and Surgery in India for Ethiopians
- Robotic Cancer Surgery in India for Ethiopians
- Scoliosis Surgery in India for Ethiopians