

Choosing the Best Parkinson's DBS Treatment Team and Hospital in India: A Guide for Ethiopian Patients
DBS surgery doesn't end when the electrodes are implanted. The device then needs specialised programming, adjusted over months and, often, years, by a movement disorder neurologist using dedicated software most patients won't have access to once they're home. A centre's plan for that ongoing programming matters as much as the surgery's own precision.
Most patients researching DBS surgery in India spend the bulk of their time comparing prices, and understandably so — cost is often what makes the trip possible at all. But price is the easiest variable to compare and, on its own, the least useful one for predicting whether the treatment actually controls symptoms well, months and years after the operation itself. Two quotes that look identical on paper can represent very different plans for what happens after the surgery is finished. This matters more for DBS than for almost any other procedure, because DBS is fundamentally a two-phase treatment. The surgery places electrodes with extreme precision into specific, tiny targets deep in the brain, but the device only becomes genuinely effective through programming, adjusting stimulation settings across multiple visits in the weeks after surgery, and periodically for years afterward as the disease progresses. This programming is performed not by the surgeon but by a movement disorder neurologist with specific DBS programming expertise and dedicated equipment, and it is a genuinely distinct skill from the surgical implantation itself. Because this specialised programming access essentially doesn't exist in Ethiopia, planning honestly for how ongoing adjustments will happen once a patient returns home, whether through an extended stay in India, remote programming where genuinely available, or coordination with a visiting specialist, is as consequential as the surgery's own precision, and this planning is easy to overlook when a patient focuses only on the operation itself. In 24 years of arranging medical care in India for patients across Africa and Asia, asking directly how programming will continue for years, not just weeks, is the single most useful question in this entire process. The two decisions, treatment team and hospital, deserve equal weight. A skilled team without the right hospital infrastructure behind them, and a well-equipped hospital without a team genuinely experienced in both surgery and long-term programming, can each independently produce a disappointing result. What follows is a practical guide to evaluating both, together with the other factors that quietly shape how well the entire journey goes.
Healing Journeys of Ethiopian Patients






Key Takeaways
- The guide explains that DBS is a two-phase treatment: precise electrode implantation followed by specialised programming that may continue for months and years. Because dedicated DBS programming access is limited in Ethiopia, patients should establish a realistic long-term programming plan before travelling.
- The page 2 graphic gives equal 50% weighting to the treatment team and hospital, meaning both should be independently assessed. The team should include an NMC-registered neurosurgeon and movement disorder neurologist with dedicated DBS training and experience in both implantation and programming.
- The page 3 chart illustrates increasing accurate electrode-placement and complication-free rates with higher DBS volume, from 78% for fewer than 15 cases annually to 96% for 60+ cases. The guide therefore recommends checking the team's specific annual DBS implantation volume rather than relying on general neurosurgical or neurological experience.
- Hospital assessment focuses on NABH or JCI accreditation, a dedicated movement-disorder programme, advanced stereotactic targeting technology and a written programming schedule. The page 4 graphic presents illustrative precisely targeted, uncomplicated outcomes of 77% without formal accreditation, 88% with NABH and 95% with JCI.
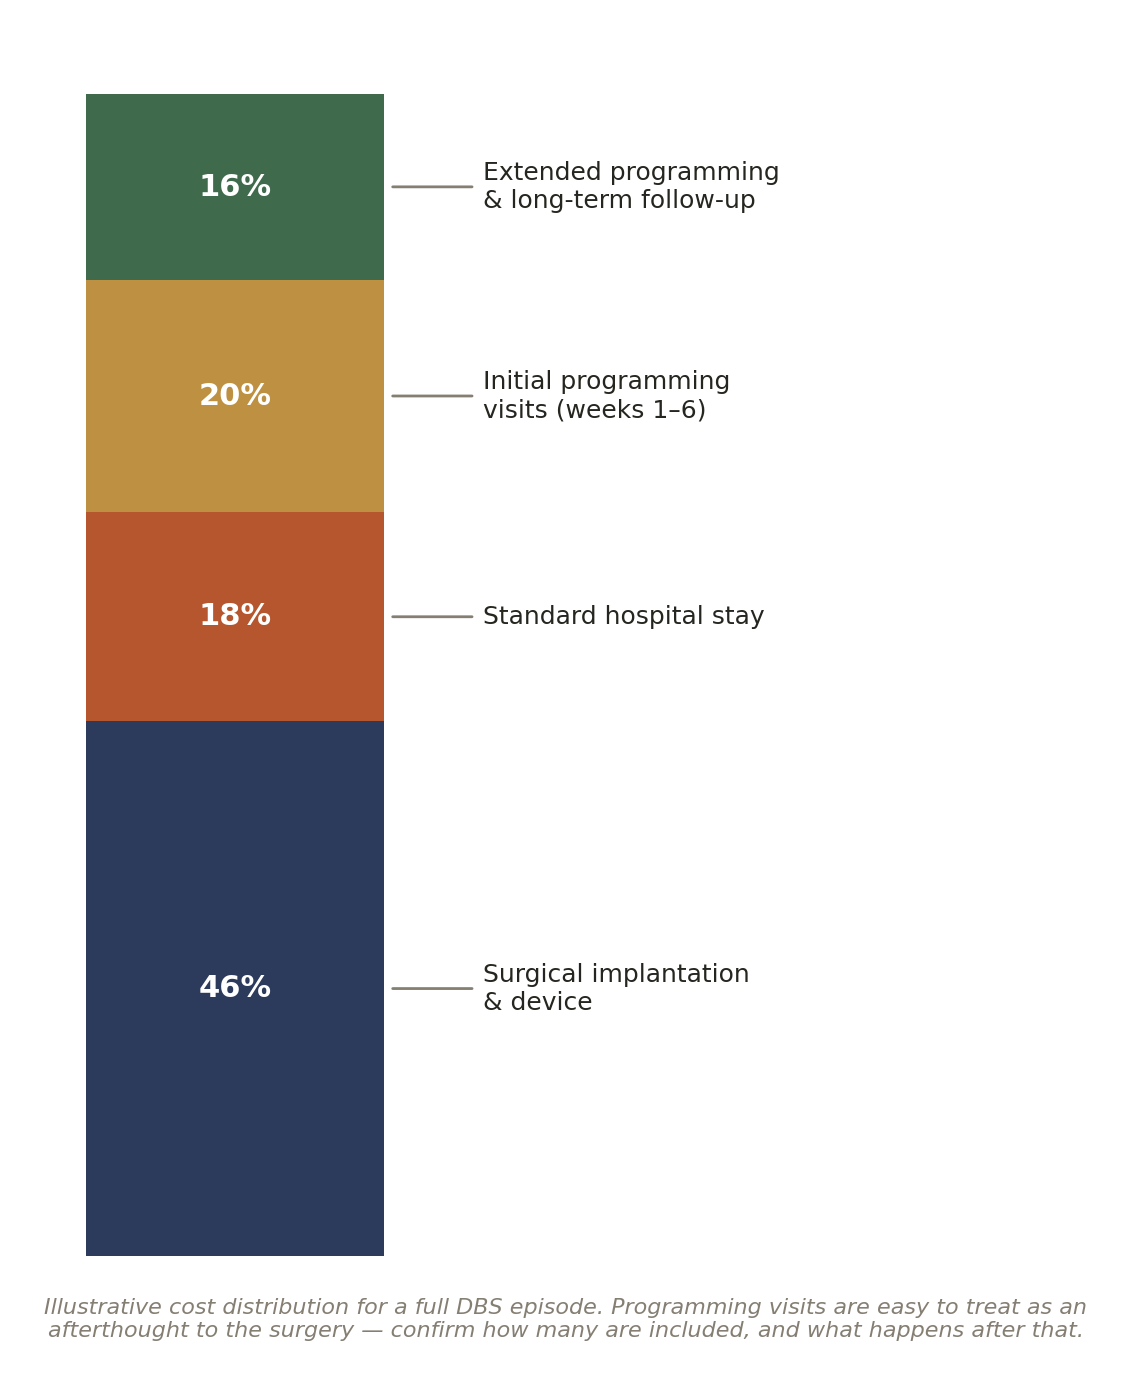
- The page 6 cost graphic illustrates an indicative DBS episode with 46% for surgical implantation and device, 18% for standard hospital stay, 20% for initial programming visits and 16% for extended programming and long-term follow-up. The guide recommends requesting an itemised estimate that includes the full course of programming rather than treating it as an afterthought.
- For Ethiopian patients, the guide recommends a second opinion on DBS candidacy, independent credential verification, medication-response assessment, a written post-operative programming schedule and a multi-year programming plan after returning to Ethiopia. A named follow-up contact should also be confirmed before treatment.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
- Treatment
- Parkinson’s DBS Treatment
- Patients
- Ethiopian Patients
- Key Specialists
- DBS Neurosurgeon and Movement Disorder Neurologist
- Decision Weighting
- Treatment Team 50% / Hospital 50%
- First Step
- Confirm whether DBS is genuinely appropriate for the patient's symptoms
- Candidacy Check
- Parkinson’s medication response and symptom assessment
- DBS Check
- Dedicated team experience and annual DBS volume
- Targeting
- Advanced stereotactic targeting technology
- Programming
- Structured post-operative programming schedule
- Accreditation
- NABH or JCI
- Cost Check
- Surgery, device and all programming visits
- Second Opinion
- Recommended before travelling
- Follow-Up
- Multi-year programming plan in Ethiopia
- Key Warning
- Do not choose DBS based only on the surgical price
- Decision Principle
- Choose a complete DBS programme with strong surgery and long-term programming support.
In Brief
For Ethiopian patients considering DBS treatment in India, the guide recommends evaluating the entire DBS programme rather than the implantation surgery alone. Patients should verify candidacy, team-specific DBS experience, stereotactic targeting technology, programming support, transparent costs and a realistic long-term programming plan in Ethiopia.
01 The DBS Treatment Team in India: What Actually Matters
The treating neurosurgeon and movement disorder neurologist's qualifications are the starting point, not the finish line. The following, taken together, give a genuinely reliable picture of the whole team.
Registration and formal qualification, for both specialists involved. Confirm both the neurosurgeon and the movement disorder neurologist are registered with the National Medical Commission of India (NMC), and hold the relevant postgraduate qualifications with dedicated DBS training. This is independently verifiable through the NMC's public Indian Medical Register and is worth checking directly rather than taking on trust.
Genuine, dedicated DBS experience across the team. Ask specifically how much of the team's regular practice, both surgical implantation and ongoing programming, is dedicated to DBS specifically, not general neurosurgery or general neurology.
Case volume, specifically in DBS implantation. Ask directly how many DBS procedures the team performs each year. Targeting precision and long-term outcomes are closely tied to this specific experience.
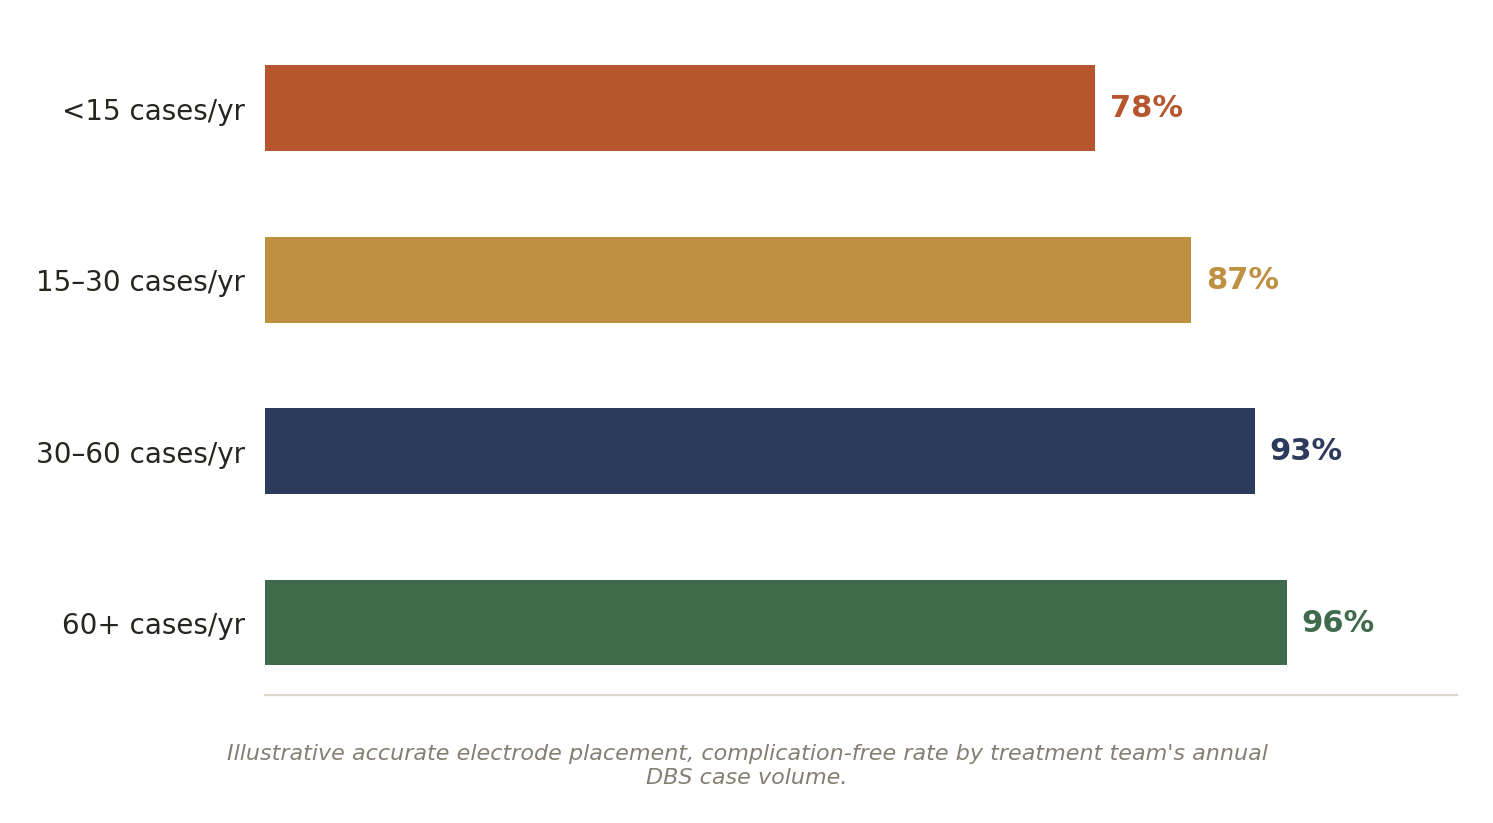
Why case volume matters for both the precision of placement and the confidence of programming that follows.
A rigorous, honest candidacy assessment. Ask specifically what testing, including response to Parkinson's medication, was used to assess whether DBS is genuinely likely to help your specific symptoms, since DBS helps some symptoms more reliably than others.
A clear plan for multiple post-operative programming visits, not just one. Ask how many programming sessions are typically needed in the weeks after surgery, and how the team plans for this before you ever travel, since this phase is where the treatment's real effectiveness is determined.
Transparency about outcomes and experience with international patients. A team willing to discuss their own targeting precision and long-term symptom control outcomes candidly, and who is accustomed to patients travelling from Ethiopia and the wider region, is showing exactly the accountability worth trusting.
02 The DBS Hospital in India: What Actually Matters
The hospital is not simply a venue for the team's work; because DBS's real effectiveness depends on programming continuing for years, the hospital's long-term systems matter as much as its surgical precision.
Accreditation. National Accreditation Board for Hospitals & Healthcare Providers (NABH) accreditation is the baseline worth confirming for any hospital under consideration; Joint Commission International (JCI) accreditation, held by a smaller number of leading Indian hospitals, reflects an internationally benchmarked standard of safety and quality worth actively seeking out.
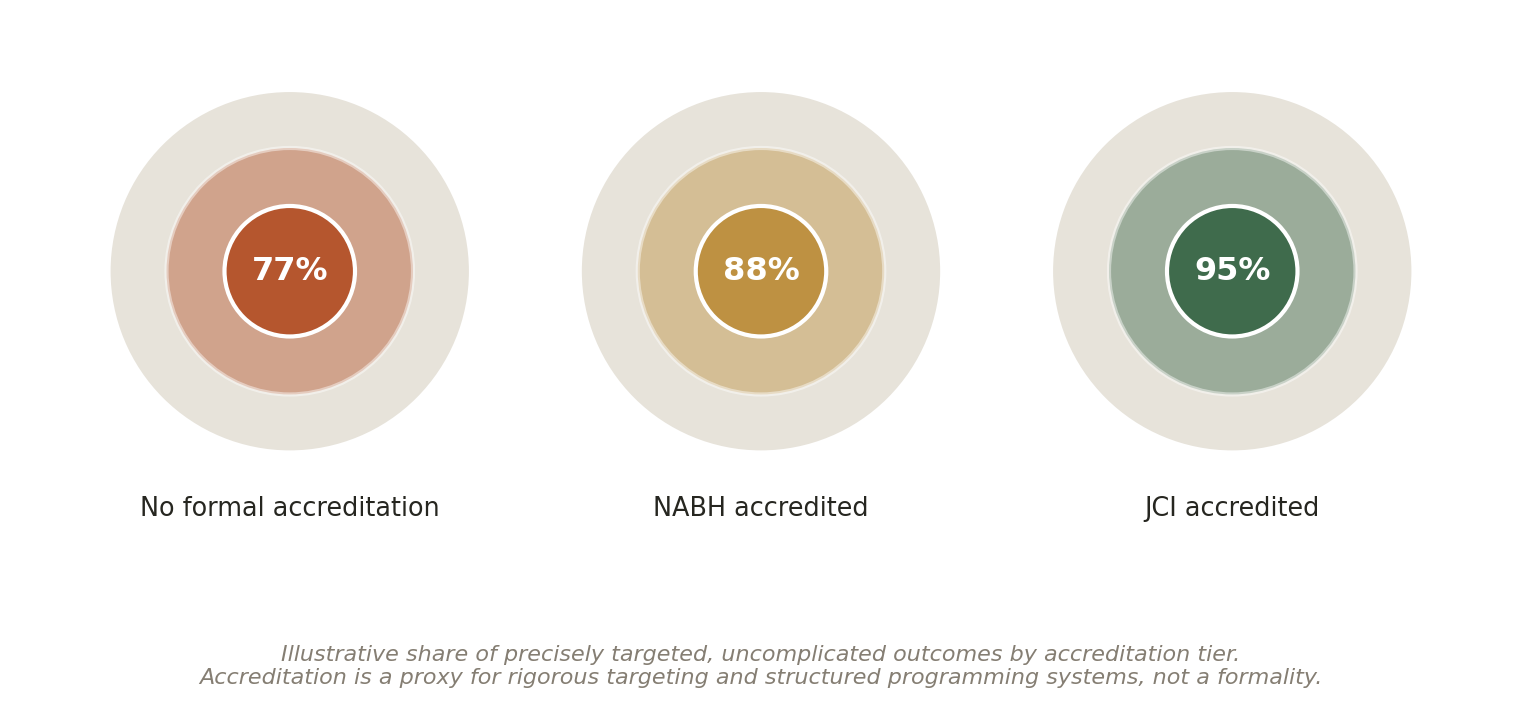
Accreditation is a proxy for rigorous targeting and structured programming systems, not a formality.
A genuinely dedicated movement disorder neurology programme. Confirm the hospital has a movement disorder neurologist with specific DBS programming expertise, separate from the surgical team, since this is the specialist who will shape the treatment's actual effectiveness over time.
Advanced imaging and stereotactic targeting technology. Confirm the hospital has genuine, modern capability for precise electrode targeting, since this technology directly affects placement accuracy.
A written, structured programming schedule. Ask for the hospital's standard post-operative programming protocol in writing, including the number of planned visits and the typical timeline.
A genuine plan for remote or long-distance programming support, where available. Ask specifically whether the hospital offers any form of remote programming adjustment for patients who have returned home, and what this genuinely involves.
International patient services. A dedicated international patient department, offering visa support, airport coordination, interpreter or Amharic-speaking liaison support, and clear pre-departure communication, is a meaningful sign that the hospital is genuinely set up for patients travelling from Ethiopia, not simply willing to accept them.
03 Other Factors in India That Quietly Shape the Outcome of DBS Treatment
Beyond the treatment team and the hospital individually, a handful of practical factors determine how smoothly the whole process, and the years of programming that follow, actually go.
A genuine second opinion. Before committing to travel, it is worth having a second specialist review your case and confirm, specifically, whether DBS is genuinely likely to help your particular symptoms.
Independent credential verification. Do not rely solely on a hospital's own marketing material. Cross-check both specialists' registration on the NMC's Indian Medical Register, and the hospital's accreditation status through the NABH or JCI's own public directories.
Full cost transparency, including all programming visits. Ask for a single, detailed, itemised estimate covering the surgery, device, and the full course of initial programming visits, since these are sometimes quoted separately in a way that understates the true total cost.
Clear communication throughout an extended stay. Confirm who your point of contact will be across the surgery and the weeks of programming that follow, and that this person can communicate clearly with you throughout, not only through a general enquiries line.
A concrete plan for the years of programming ahead. Ask specifically and honestly how adjustments will be managed once you are back in Ethiopia for good, since this is a multi-year commitment, not a single trip, and deserves a clear plan from the outset.
Why this balance matters in practice: a genuinely skilled surgical team operating without a genuine long-term programming plan behind them, and a state-of-the-art hospital without a team willing to be honest about DBS candidacy, can each still produce a disappointing result. The strongest choice is where both are independently verified to be excellent, not one compensating for the other.
A practical checklist before you commit
- Neurosurgeon and movement disorder neurologist NMC
- registration verified independently
- Team's dedicated DBS experience confirmed
- Team's specific annual DBS case volume confirmed
- Hospital's NABH or JCI accreditation verified independently
- Candidacy assessment, including medication response testing, confirmed
- Dedicated movement disorder neurologist for programming confirmed
- Advanced stereotactic targeting technology confirmed
- Written, structured post-operative programming schedule
- requested
- Second opinion obtained on DBS candidacy specifically
- Full itemised cost estimate including all programming visits requested
- Long-term, multi-year programming plan for Ethiopia confirmed
- Named post-discharge follow-up contact confirmed
A closing word
Send your diagnosis, current medications, and a description of your specific symptoms. I will help you compare specific treatment teams and hospitals against these exact criteria, so the decision rests on verified substance rather than the most polished website or the lowest number on a quote.
Sources
- 🌐 National Medical Commission of India — Indian Medical Register, for verifying a specialist's qualification and registration
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH), Quality Council of India
- 🌐 Joint Commission International — directory of JCI-accredited organisations worldwide
- 🌐 The relationship between pre-operative medication response and DBS candidacy, and the critical role of structured
Frequently Asked Questions by Ethiopians about Parkinson's DBS Treatment Teams and Hospitals in India
Why is programming important after DBS surgery?
DBS does not end with electrode implantation. Programming adjusts stimulation settings over multiple visits and may continue for years as Parkinson’s symptoms change.
How are the treatment team and hospital weighted?
The page 2 graphic assigns 50% to the treatment team and 50% to the hospital, so both should be independently evaluated.
What specialists should be part of the DBS team?
The guide recommends a DBS-experienced neurosurgeon and movement disorder neurologist, with both specialists' qualifications independently verified.
How should I assess DBS team experience?
Ask how many DBS implantations the team performs each year and how much of its practice is specifically dedicated to DBS rather than general neurosurgery or neurology.
How is DBS candidacy assessed?
The guide recommends confirming response to Parkinson’s medication and evaluating whether DBS is likely to improve the patient's specific symptoms, because DBS does not help every symptom equally.
What should the hospital provide?
The guide recommends NABH or JCI accreditation, a dedicated movement-disorder programme, advanced stereotactic targeting technology and a structured programming schedule.
Should programming costs be included in the quotation?
Yes. The guide recommends an itemised estimate covering the surgery, device and full course of initial programming visits, rather than treating programming as a separate afterthought.
Should Ethiopian patients get a second opinion?
Yes. A second specialist should specifically review whether DBS is genuinely appropriate for the patient's symptoms and treatment history before travel is arranged.
How should programming continue after returning to Ethiopia?
Patients should establish a multi-year programming plan, including how adjustments will be managed after returning home and whether remote or long-distance support is genuinely available.
What are the main warning signs?
Be cautious if there is no documented DBS candidacy assessment, no dedicated movement disorder neurologist, no written programming schedule or no clear long-term programming plan for Ethiopia.
Page Summary
This guide helps Ethiopian patients choose Parkinson’s DBS treatment teams and hospitals in India by giving equal importance to the treatment team and hospital. The page 2 graphic assigns 50% to each, while page 3 highlights DBS-specific volume and electrode-placement outcomes. Page 4 focuses on accreditation, stereotactic targeting and programming systems, while page 6 highlights the cost of programming and long-term follow-up. Page 7 provides the final verification checklist.
Citation Block
| Topic | Information |
|---|---|
| Topic | Selecting Parkinson’s DBS Treatment Teams and Hospitals in India for Ethiopian Patients |
| Treatment | Deep Brain Stimulation for Parkinson’s |
| Patients | Ethiopian Patients |
| Key Specialists | DBS Neurosurgeon and Movement Disorder Neurologist |
| Decision Weighting | Treatment Team 50% / Hospital 50% |
| Candidacy | Medication response and symptom assessment |
| Team Criteria | NMC registration, DBS training and dedicated DBS experience |
| Case Volume | Annual DBS implantation volume |
| Targeting | Advanced stereotactic targeting technology |
| Programming | Written, structured post-operative schedule |
| Hospital Criteria | NABH/JCI and dedicated movement-disorder programme |
| Cost Transparency | Surgery, device and all programming visits |
| Second Opinion | Recommended for DBS candidacy |
| Follow-Up | Multi-year programming plan in Ethiopia |
| Warning Signs | No candidacy assessment, unclear programming plan or incomplete cost estimate |
| Key Decision | Choose the complete DBS treatment and programming programme |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Ethiopia










Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Ethiopia who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Eritrea
- Djibouti
- Somalia
- Kenya
- Sudan
- Burundi
- Comoros
- Ethiopia
- Madagascar
- Malawi
- Mauritius
- Mozambique
- Rwanda
- South Sudan
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Ethiopia to India: Your Complete Patient Support Guide
- Brain Tumour Surgery in India for Ethiopians
- Cancer Treatment in India for Ethiopians
- Cardiac Surgery in India for Ethiopian Patients
- Cervical and Disc Replacement Surgery in India for Ethiopians
- Cosmetic and Plastic Surgery in India for Ethiopians
- CyberKnife Treatment in India for Ethiopians
- Eye Surgery in India for Ethiopians
- Gamma Knife Treatment in India for Ethiopians
- Heart Valve Replacement Surgery in India for Ethiopians
- Hip Surgery in India for Ethiopian Patients
- Knee Surgery in India for Ethiopian Patients
- Laparoscopic and Robotic Myomectomy Surgery in India for Ethiopians
- Neurosurgery in India for Ethiopians
- Paediatric Cardiac Surgery in India for Ethiopians
- Paediatric Neurosurgery in India for Ethiopians
- Prostate Cancer Treatment and Surgery in India for Ethiopians
- Robotic Cancer Surgery in India for Ethiopians
- Scoliosis Surgery in India for Ethiopians