

Selecting the Best Pancreatic Cancer Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
Only seven in a hundred Kenyan pancreatic cancer patients reach the operation that could cure them — and the window for it closes fast.
Pancreatic cancer is unforgiving in a way few other cancers are, because the window for a genuinely curative operation is narrow, and it closes fast. The Whipple procedure, a complex surgery removing the head of the pancreas along with parts of the small intestine, bile duct, and sometimes stomach, remains the only treatment that offers a real chance of cure, but only if the tumour is caught before it has grown into surrounding blood vessels or spread elsewhere. Across 24 years of guiding international patients through Indian hospitals, this is a cancer where the decision of where to seek a second opinion can be the decision that determines whether curative surgery is still possible at all. This is the framework I use when a Kenyan patient with pancreatic cancer is weighing surgery in India. It follows the surgeon-then-hospital structure of this series, and opens with a statistic that should prompt an urgent second opinion for anyone told their pancreatic cancer is inoperable.
Healing Journeys of Kenyan Patients






Key Takeaways
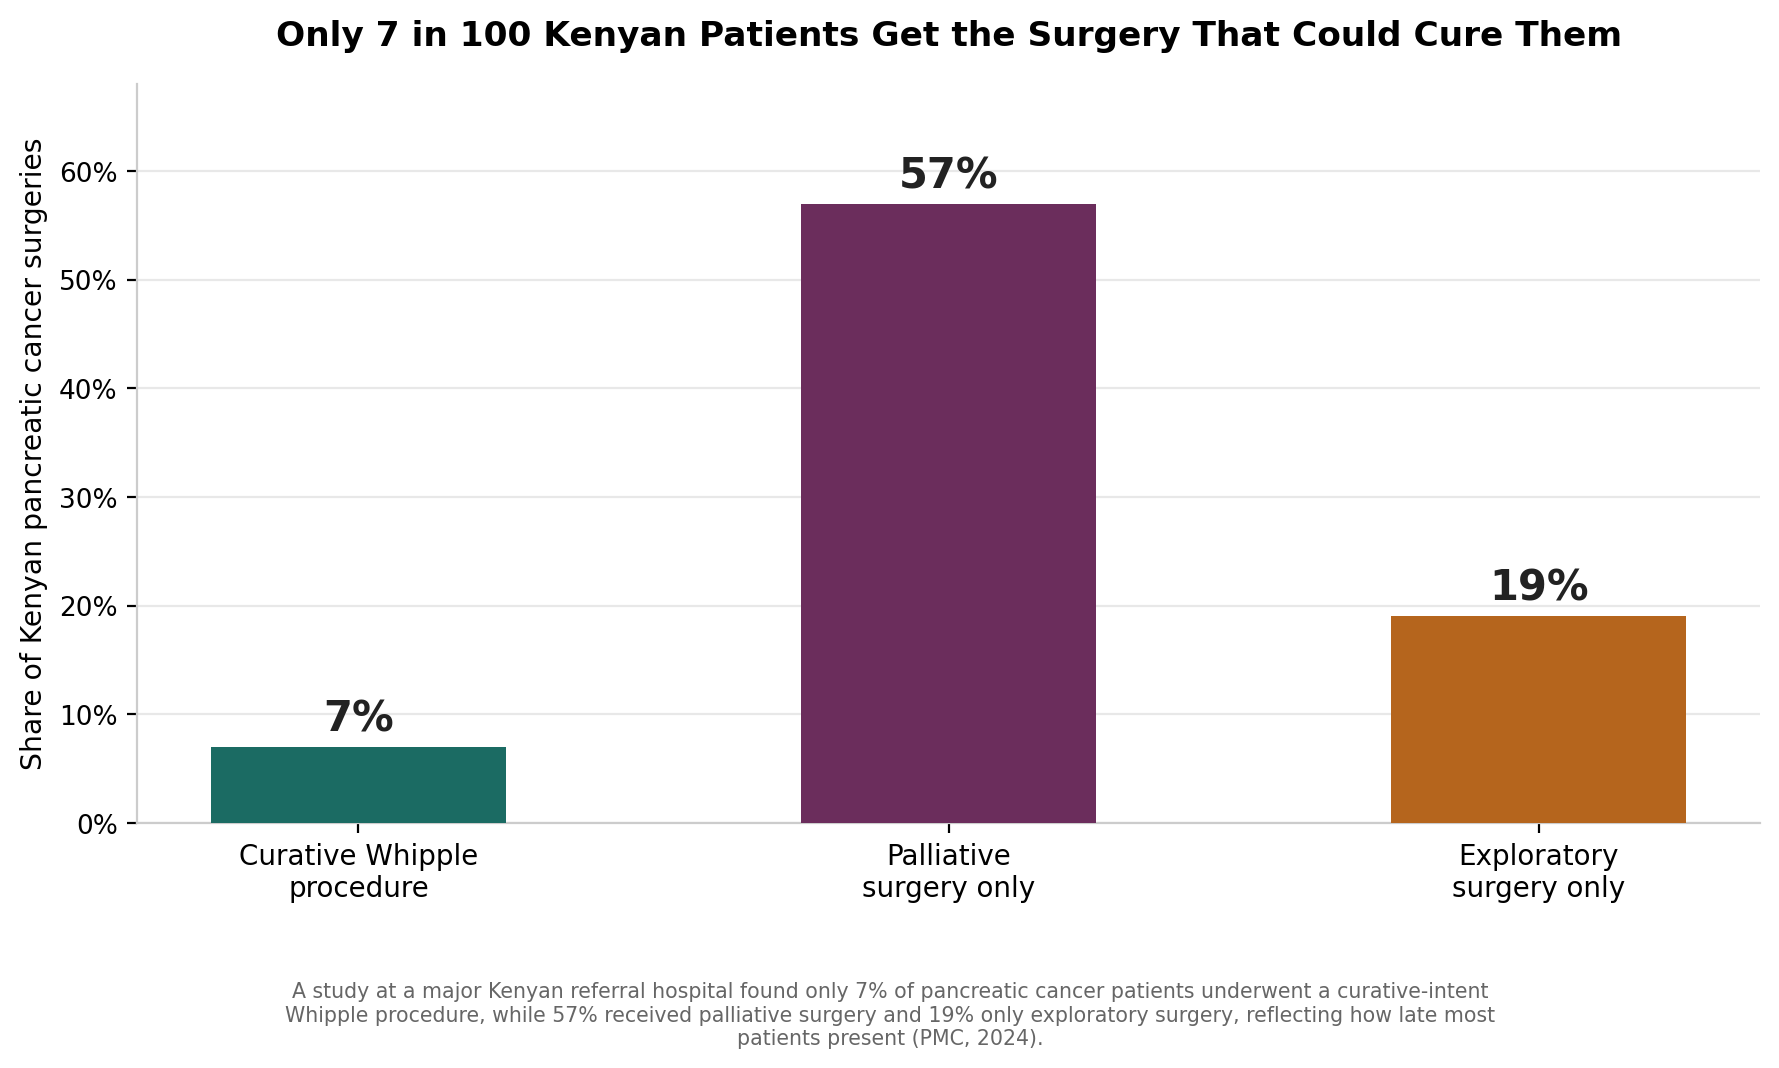
- The guide highlights the limited proportion of Kenyan pancreatic cancer patients who receive potentially curative surgery. A study at a major Kenyan referral hospital found that only 7% received a curative-intent Whipple procedure, while 57% underwent palliative surgery and 19% exploratory surgery; 54% were already metastatic at diagnosis.
- A diagnosis of “inoperable” or “unresectable” pancreatic cancer may deserve a second opinion from a high-volume pancreatic surgery centre. The guide explains that resectability can depend on surgical expertise, particularly the ability to perform vascular reconstruction when a tumour involves nearby blood vessels.
- The Whipple procedure remains the key potentially curative operation for pancreatic cancer involving the pancreatic head when the disease is appropriately resectable. The guide recommends choosing a surgeon based on personal Whipple experience, rather than general surgical or oncology experience, and asking for an imaging-based explanation of whether the tumour can be removed.
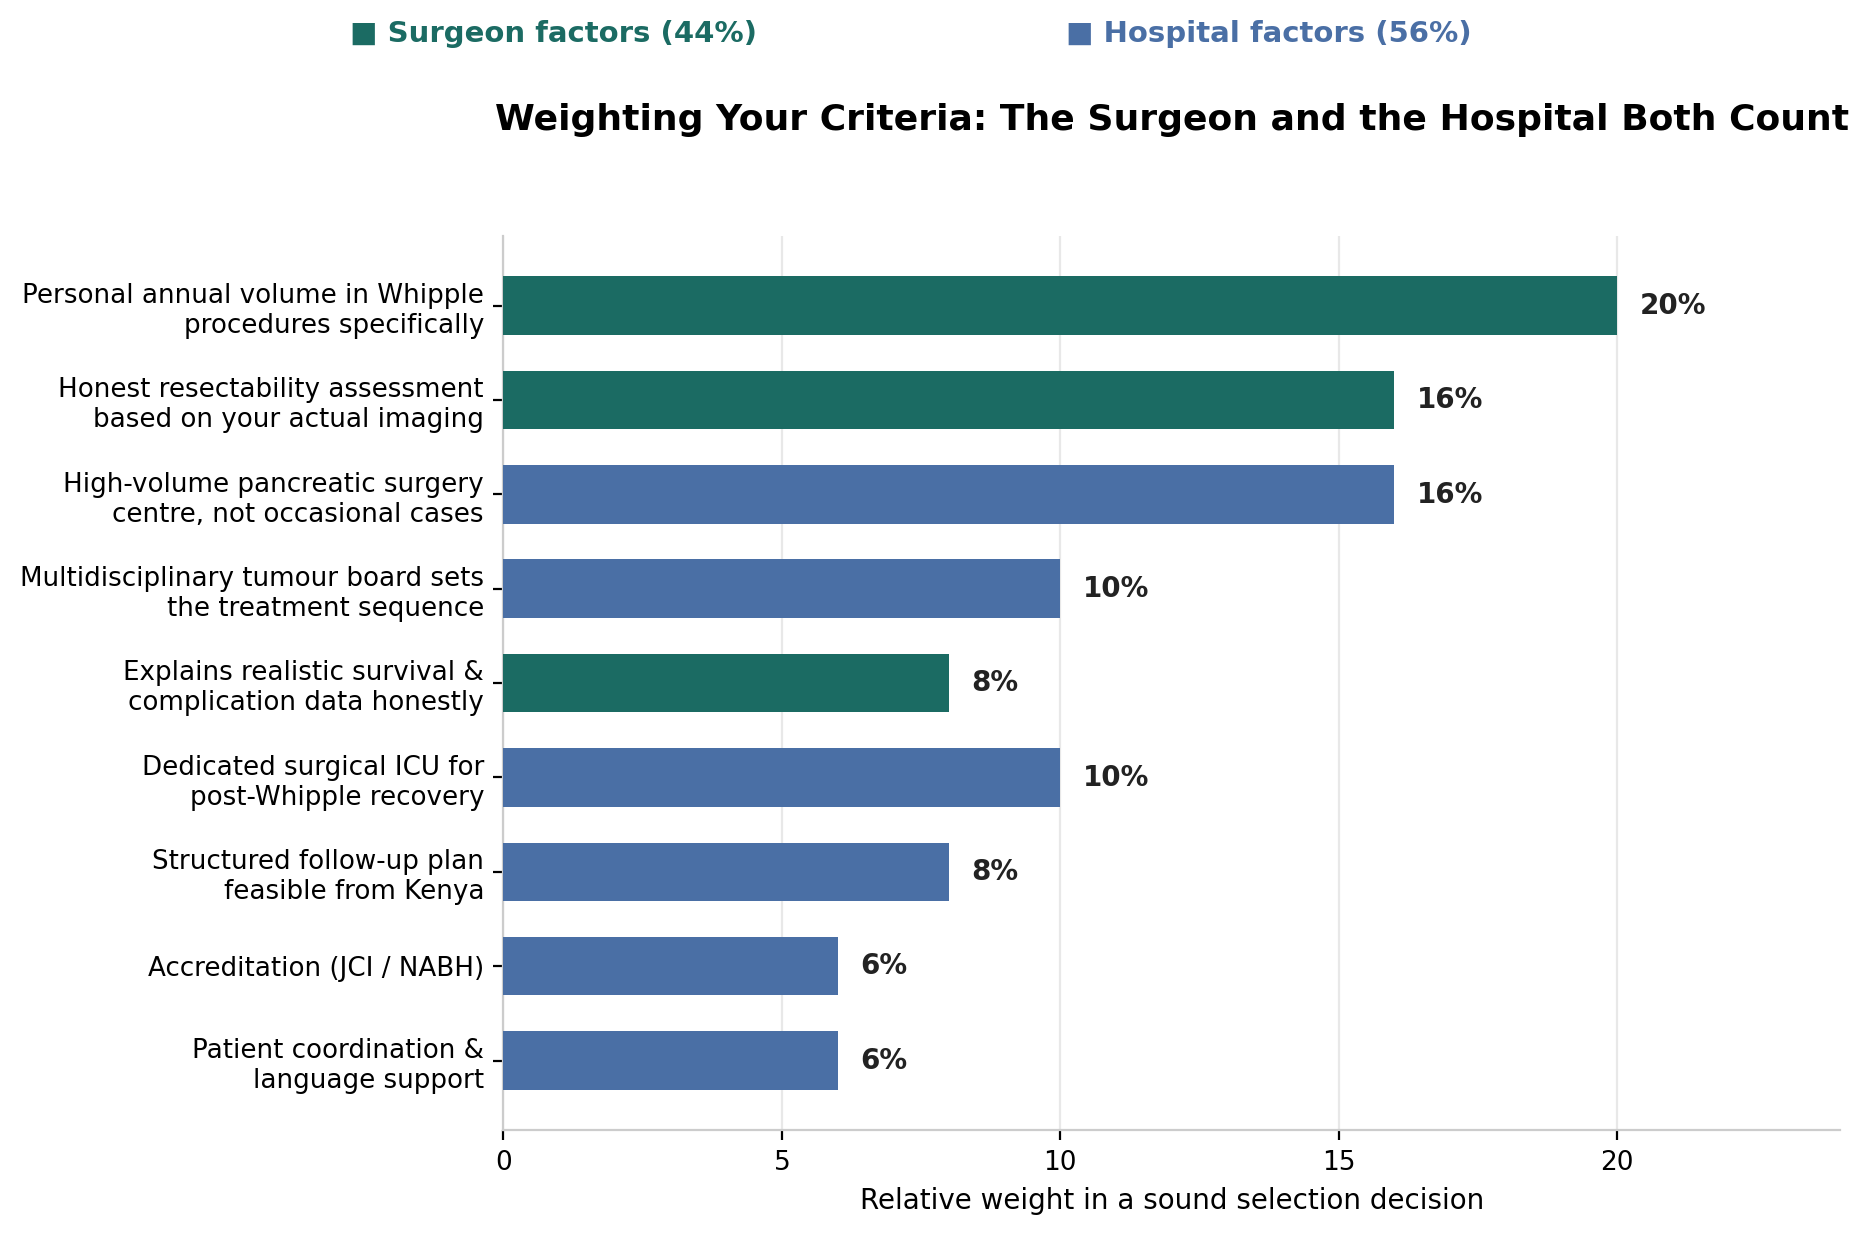
- The page 3 weighting chart assigns 44% to surgeon factors and 56% to hospital factors. Personal annual Whipple volume receives the highest individual weighting at 20%, followed by an honest imaging-based resectability assessment at 16% and a high-volume pancreatic surgery centre at 16%.
- The hospital should have a multidisciplinary tumour board, dedicated surgical ICU for post-Whipple recovery and structured follow-up that can continue in Kenya. The guide also stresses that JCI/NABH accreditation is useful for safety and infection-control screening but does not by itself prove pancreatic surgery subspecialty expertise.
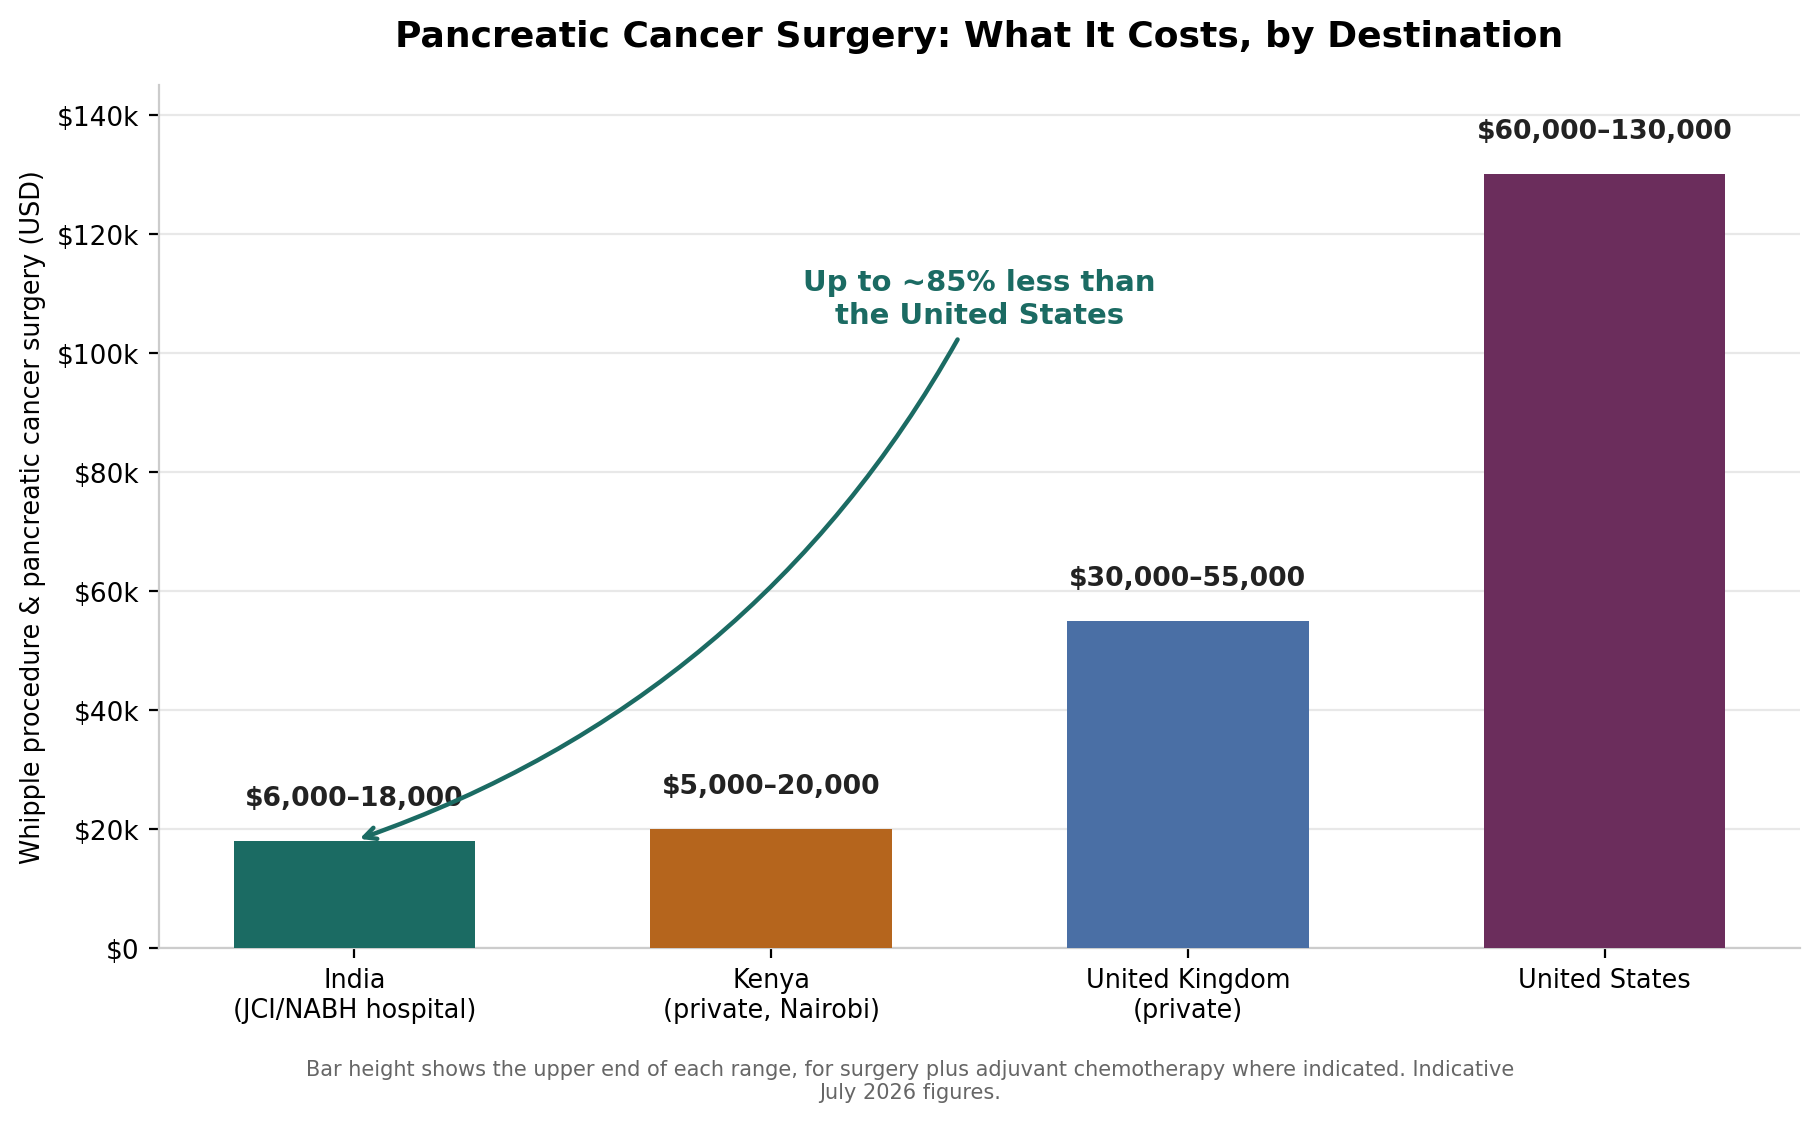
- The page 4 cost chart gives an indicative range of US$6,000–18,000 in India, compared with US$5,000–20,000 in Kenya, US$30,000–55,000 in the UK and US$60,000–130,000 in the US. Patients should confirm ICU days, adjuvant chemotherapy where indicated and all exclusions in the quotation.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years of Experience
- Treatment
- Pancreatic Cancer Surgery
- Patients
- Kenyan Pancreatic Cancer Patients
- Key Specialist
- Pancreatic / Hepatobiliary Surgeon
- Main Assessment
- Tumour stage, location and resectability
- Key Priority
- Determine whether curative-intent surgery is possible
- Key Procedure
- Whipple Procedure
- Key Selection Factor
- Personal annual Whipple volume
- Advanced Expertise
- Vascular reconstruction for selected borderline cases
- Hospital Requirement
- High-volume pancreatic surgery centre
- Multidisciplinary Care
- Surgical oncology, medical oncology and radiology
- India Cost
- Approximately US$6,000–18,000
- Kenya Cost
- Approximately US$5,000–20,000
- UK Cost
- Approximately US$30,000–55,000
- US Cost
- Approximately US$60,000–130,000
- Pre-Travel Records
- Complete CT/MRI staging scans and biopsy results
- Follow-Up
- Written imaging and oncology follow-up plan in Kenya
- Key Warning Signs
- Inoperable diagnosis without direct imaging review or no vascular reconstruction capability
- Decision Principle
- Confirm resectability at a high-volume pancreatic surgery centre before accepting a non-curative treatment pathway
In Brief
For Kenyan patients with pancreatic cancer, the guide recommends seeking a high-volume pancreatic surgery second opinion, particularly after an “inoperable” diagnosis. Personal Whipple volume, direct review of CT/MRI imaging, vascular reconstruction capability and multidisciplinary treatment planning are key factors. The guide gives an indicative cost of US$6,000–18,000 in India for the Whipple procedure and associated care.
Before the surgeon: only seven in a hundred get the operation that could cure them
A study at a major Kenyan referral hospital found that of pancreatic cancer patients who underwent surgery, only 7% received a curative-intent Whipple procedure. The majority, 57%, received palliative surgery aimed at relieving symptoms rather than curing the disease, and 19% underwent exploratory surgery alone, meaning the tumour was found to be inoperable once surgeons could see it directly. The same study found 54% of patients were already metastatic at diagnosis, with a median survival of just 3 months and a one-year survival rate of 32%.
This pattern is consistent across the region, driven substantially by late-stage presentation and limited access to the imaging needed to catch pancreatic cancer while it's still resectable. But it's worth being precise about what "inoperable" actually means, because the threshold for resectability isn't fixed. It depends heavily on the surgical team's experience with vascular reconstruction, since tumours that appear to invade nearby blood vessels can sometimes still be removed by a surgeon skilled in reconstructing those vessels, an option not available at every centre. Patients who underwent surgical resection had a dramatically better survival outcome than those who didn't in the Kenyan cohort, underlining how much this decision matters.
The practical takeaway is that a diagnosis of "inoperable" or "unresectable" pancreatic cancer deserves a second opinion from a genuinely high-volume pancreatic surgery centre before treatment shifts entirely to palliative care, since resectability assessments vary meaningfully by surgical experience, not just tumour biology.
Should you travel at all?
Kenya's major hospitals manage pancreatic cancer diagnosis and can perform palliative procedures competently, and for patients whose disease is genuinely, unambiguously metastatic, where surgery of any kind wouldn't change the outcome, treatment and supportive care in Kenya is appropriate.
For any patient told their tumour might be borderline resectable or inoperable, and for anyone being offered a Whipple procedure at a centre with limited volume in this specific surgery, India is where I steer patients, confidently, for a second opinion at minimum. India's high-volume pancreatic surgery centres perform Whipple procedures routinely, with surgeons experienced in the vascular reconstruction techniques that can convert a borderline case into a genuinely resectable one, at a fraction of UK or US cost.
Part one: judging the surgeon
1. Personal annual volume in Whipple procedures specifically
I weight this above every other factor, and the chart below reflects that. Ask how many Whipple procedures the surgeon personally performs each year, since this single number correlates more strongly with outcomes than almost any other factor in pancreatic surgery.
2. An honest resectability assessment based on your actual imaging
Ask the surgeon to review your specific imaging and explain, precisely, why your tumour is or isn't resectable, rather than accepting a general "inoperable" label passed along from elsewhere.
3. Explains realistic survival and complication data honestly
Ask what realistic survival looks like for your specific stage and tumour characteristics, and what the surgeon's own complication rates are for this procedure.
Part two: judging the hospital
For pancreatic surgery, institutional volume carries as much weight as the individual surgeon, reflected in the balance above, because Whipple procedure outcomes are strongly tied to how often the whole surgical and ICU team performs this specific operation together.
4. A high-volume pancreatic surgery centre, not occasional cases
Ask how many Whipple procedures the hospital performs annually as an institution, not just the individual surgeon, since post-operative complication management depends on a whole team's experience.
5. A multidisciplinary tumour board sets the treatment sequence
Ask whether your case is reviewed by a team including surgical oncology, medical oncology, and radiology, confirming resectability and treatment sequence before committing to surgery.
6. A dedicated surgical ICU for post-Whipple recovery
Ask about ICU capacity and protocols specifically for pancreatic surgery recovery, since this remains one of the more complex post-operative courses in abdominal surgery.
7. A structured follow-up plan feasible from Kenya
Ask what the follow-up imaging schedule looks like, and how adjuvant chemotherapy, if needed, will be coordinated with your care in Kenya afterward.
8. Accreditation, read properly
JCI and NABH accreditation are meaningful filters on safety and infection control, but say nothing about pancreatic surgery sub-specialisation specifically. Use accreditation to exclude weak candidates, not to choose between the
strong ones.
9. The cost you will actually pay
Let me be emphatic about this, because 24 years of handling these cases has taught me nothing more consistently: disputes almost never concern the quoted price. They concern what the quote silently omitted. For pancreatic surgery specifically, insist the estimate states how many ICU days are included, and whether adjuvant chemotherapy, if indicated, is part of the package.
Budget beyond the surgery. Direct Nairobi–Delhi and Nairobi–Mumbai flights run roughly 550 to 850 dollars return, and recovery from a Whipple procedure typically requires two to three weeks in India before you're fit to travel home.
Four signals that should make you pause
Certain patterns reliably precede a difficult outcome. A surgeon who cannot state personal volume in Whipple procedures specifically. A resectability opinion given without reviewing your actual imaging directly. No mention of vascular reconstruction capability for borderline cases. And a hospital unable to describe its dedicated pancreatic surgery ICU protocols.
None alone proves a bad hospital. Together they warrant a second opinion before you accept an "inoperable" diagnosis as final.
The Kenya-specific practicalities

Send the full staging imaging, CT or MRI, and any biopsy results, not just a summary letter, so the surgical team can give you a genuine, imaging-based resectability opinion before you travel.
Direct Nairobi–Delhi and Nairobi–Mumbai flights make this roughly a six-hour journey. The Indian medical e-visa is issued within three to five working days against a hospital letter, and an attendant can travel with you.
Agree in advance on a written follow-up imaging schedule your Kenyan oncologist can act on, since ongoing surveillance after pancreatic surgery continues for years.
The questions I would ask before committing
Of the surgeon:
- How many Whipple procedures do you personally perform each year?
- Having reviewed my actual imaging, why is my tumour resectable or not?
- What is my realistic survival, and what are your personal complication rates?
Of the hospital:
- How many Whipple procedures does this hospital perform annually?
- Is my case reviewed by a full multidisciplinary tumour board?
- What is your dedicated ICU protocol for pancreatic surgery recovery?
- What exactly is excluded from the quoted price?
- May I speak to a previous East African patient treated for pancreatic cancer here?
A team that answers all eight without irritation is very likely the right team. One that turns vague at the first or second has told you what you needed to know at no cost at all.
Straight Answers for Kenyan Patients about Pancreatic Cancer Surgeons and Hospitals in India
Why do so few Kenyan pancreatic cancer patients get curative surgery?
A study at a major Kenyan referral hospital found only 7% of surgical patients received a curative Whipple procedure, with 54% already metastatic at diagnosis, reflecting both late presentation and limited access to the specialised imaging and surgical expertise needed to identify and operate on resectable tumours.
How much does pancreatic cancer surgery cost in India for a Kenyan patient?
Typically 6,000 to 18,000 US dollars for the Whipple procedure and associated care. The same surgery runs roughly 5,000 to 20,000 dollars in Kenya, 30,000 to 55,000 in the UK, and 60,000 to 130,000 in the US.
I was told my pancreatic cancer is inoperable. Should I get a second opinion?
Yes, strongly consider it, particularly if the opinion came from a centre with limited experience in pancreatic surgery. Resectability assessments vary meaningfully by surgical team experience, especially for tumours near major blood vessels, where skilled vascular reconstruction can sometimes convert a borderline case into an operable one.
What is the Whipple procedure?
It's a complex surgery removing the head of the pancreas, part of the small intestine, the gallbladder, and part of the bile duct, then reconstructing the digestive tract. It remains the only treatment offering a genuine chance of cure for pancreatic cancer confined to the pancreatic head.
Why does surgical volume matter so much for this specific procedure?
The Whipple procedure has one of the steepest volume-outcome relationships in surgery; centres and surgeons performing it frequently have significantly lower complication and mortality rates than those doing it occasionally, because managing the complex post-operative course requires genuine institutional experience.
What symptoms suggest pancreatic cancer should be investigated urgently?
Painless jaundice, unexplained weight loss, new-onset diabetes in someone without risk factors, and persistent upper abdominal or back pain all warrant prompt imaging, since early detection is the single biggest factor in whether curative surgery remains possible.
A closing word
For a Kenyan patient with pancreatic cancer, the gap between what's technically resectable and what gets labelled inoperable often comes down to surgical volume and vascular reconstruction experience, not tumour biology alone, and India offers exactly the high-volume expertise that can close that gap, at a fraction of UK or US cost. The best surgeon is the one whose Whipple-specific volume and honest, imaging-based resectability opinion show he's assessing your actual tumour, not a general label. The best hospital pairs him with the institutional ICU experience this surgery genuinely demands. If you would like me to look at your imaging and talk through honestly whether a second opinion could change your options, send them across.
Sources
- 🌐 Clinicopathologic characteristics and treatment outcomes of pancreatic cancer patients at a tertiary referral hospital in Kenya. PMC, 2024
- 🌐 The Current Landscape of Pancreatic Cancer Management in Sub-Saharan Africa – A Perspective Review. PMC. pmc.ncbi.n
- 🌐 Clinical Presentation and Management Outcomes of Pancreatic Cancer in African Countries: A Scoping Review. PubMed. pu
- 🌐 National Medical Commission of India — surgeon and specialist registration verification
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH) — accredited hospital directory
Frequently Asked Questions by Kenyans about Pancreatic Cancer Surgeons and Hospitals in India
Why is pancreatic cancer surgery particularly urgent?
The guide explains that the window for potentially curative surgery can be narrow. Early assessment of resectability is therefore important before the disease progresses or spreads.
How many Kenyan patients in the cited study received a curative Whipple?
Only 7% of pancreatic cancer patients who underwent surgery received a curative-intent Whipple procedure, while 57% received palliative surgery.
I was told my pancreatic cancer is inoperable. Should I seek another opinion?
The guide strongly recommends considering a second opinion, particularly if the original assessment came from a centre with limited pancreatic surgery volume or did not involve direct review of the patient's imaging.
What is the Whipple procedure?
It is a complex operation that removes the head of the pancreas along with parts of the small intestine, bile duct and gallbladder, followed by reconstruction of the digestive tract.
Why does Whipple-specific surgical volume matter?
The guide emphasises that frequent performance of this complex operation gives the surgeon and hospital team greater experience in managing both the surgery and its potentially difficult postoperative complications.
What is vascular reconstruction in pancreatic surgery?
When a tumour involves nearby blood vessels, selected high-volume surgeons may be able to remove and reconstruct affected vessels. This can make some borderline cases potentially resectable.
What should a suitable pancreatic cancer hospital provide?
Look for a high-volume pancreatic surgery programme, multidisciplinary tumour board, dedicated surgical ICU and a structured plan for chemotherapy and follow-up.
How much does pancreatic cancer surgery cost in India?
The guide gives an indicative range of US$6,000–18,000 for the Whipple procedure and associated care. Patients should confirm exactly what the quotation includes.
What records should Kenyan patients send before travelling?
Send the complete CT or MRI staging scans and biopsy results, rather than only a summary letter, so the surgical team can provide a genuine imaging-based resectability opinion.
How should follow-up be managed after surgery in India?
Patients should agree on a written follow-up imaging schedule and coordinate any required adjuvant chemotherapy with their Kenyan oncologist, as surveillance continues after pancreatic surgery.
Page Summary
This seven-page Kenya patient guide explains how patients can evaluate pancreatic cancer surgeons and hospitals in India, with particular emphasis on Whipple-specific experience and obtaining a genuine imaging-based resectability assessment. It highlights the low proportion of curative Whipple procedures in the cited Kenyan study, explains the importance of vascular reconstruction for selected borderline cases, and compares surgeon and hospital selection factors. The page 3 chart assigns 44% to surgeon factors and 56% to hospital factors, while the page 4 cost chart compares indicative costs across India, Kenya, the UK and US. The page 5 pathway shows imaging and staging → tumour-board review → surgical planning → Whipple surgery → recovery/adjuvant treatment → follow-up in Kenya.
Citation Block
| Topic | Information |
|---|---|
| Topic | Pancreatic Cancer Surgery in India for Kenyan Patients |
| Treatment | Whipple Procedure / Pancreatic Cancer Surgery |
| Patients | Kenyan Pancreatic Cancer Patients |
| Specialist | Pancreatic / Hepatobiliary Surgeon |
| Main Assessment | Tumour stage, location and resectability |
| Key Priority | Curative-intent surgery where medically possible |
| Key Procedure | Whipple procedure |
| Surgeon Check | Personal annual Whipple volume |
| Imaging Review | Direct CT/MRI-based resectability assessment |
| Advanced Expertise | Vascular reconstruction for selected borderline cases |
| Hospital Check | High-volume pancreatic surgery centre |
| Tumour Board | Surgical oncology, medical oncology and radiology |
| ICU Requirement | Dedicated surgical ICU for post-Whipple recovery |
| India Cost | Approximately US$6,000–18,000 |
| Kenya Cost | Approximately US$5,000–20,000 |
| UK Cost | Approximately US$30,000–55,000 |
| US Cost | Approximately US$60,000–130,000 |
| Quote Check | ICU days and adjuvant chemotherapy inclusion |
| Pre-Travel Records | CT/MRI staging scans and biopsy results |
| Follow-Up | Imaging and oncology plan feasible from Kenya |
| Quality Check | JCI/NABH accreditation |
| Warning Signs | Inoperable diagnosis without direct imaging review |
| Selection Weighting | 44% surgeon factors and 56% hospital factors |
| Top Criterion | Personal Whipple volume – 20% |
| Kenya Statistic | Only 7% received a curative-intent Whipple in the cited study |
| Patient Pathway | Imaging → tumour board → surgical plan → Whipple → recovery/adjuvant therapy → Kenya follow-up |
| Decision Principle | Obtain a high-volume, imaging-based resectability opinion before accepting an inoperable diagnosis |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Kenya










Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Kenya who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Ethiopia
- Somalia
- Tanzania
- Uganda
- Seychelles
- Guinea
- Guinea-Bissau
- Liberia
- Mali
- Mauritania
- Niger
- Nigeria
- Senegal
- Togo
- South Sudan
- Sierra Leone
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Kenya to India: Your Complete Patient Support Guide
- Brain Tumour Surgery in India for Kenyan Patients
- Cancer Treatment and Surgery in India for Kenyan Patients
- Cardiac Treatment and Surgery in India for Kenyan Patients
- Heart Valve Replacement Surgery in India for Kenyan Patients
- Knee Replacement in India for Kenyan Patients
- Prostate Cancer Treatment and Surgery in India for Kenyan Patients
- Spine Treatment and Surgery in India for Kenyan Patients
- Selecting the Best Bariatric Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Cancer Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Cardiac Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Dental Surgeons and Clinics in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Hip Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Kidney Transplant Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Knee Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Liver Transplant Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Neurosurgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Prostate Cancer Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Spine Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For