

Selecting the Best Myomectomy Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
Fibroids are still treated most often by removing the uterus — if you may want children, ask why a myomectomy is not the operation on offer.
Uterine fibroids affect women of African descent at roughly two to three times the rate seen in white women, with more than 80% of African women developing them by age 50, often a decade or more earlier than their Western counterparts. For a Kenyan woman with fibroids who still wants children, the treatment decision made now shapes whether that remains possible. Across 24 years of guiding international patients through Indian hospitals, the myomectomy cases I think about most are not the technically difficult ones. They are the women who were offered a hysterectomy as the default answer to a problem that a fertility-preserving myomectomy could have solved just as effectively. This is the framework I use when a Kenyan woman is weighing myomectomy in India, whether laparoscopic, robotic, or open. It follows the surgeon-then-hospital structure of this series, and opens with a pattern specific to how fibroids are actually being treated in Kenya today.
Healing Journeys of Kenyan Patients






Key Takeaways
- The guide highlights the high burden of uterine fibroids among women of African descent, noting that more than 80% of African women may develop fibroids by age 50. It also points to a Kenyan study where hysterectomy was used in 42% of fibroid cases compared with 27% for myomectomy, making fertility preservation an important consideration for women who still want children.
- The guide does not present hysterectomy as inherently inappropriate, but stresses that myomectomy should be genuinely assessed before the uterus is removed when fertility is important. The decision should be based on the patient's fibroid number, size, location, symptoms and reproductive goals rather than a general preference for one procedure.
- For complex, multiple or large fibroids, India is presented as an option because high-volume minimally invasive gynaecology centres may offer laparoscopic and robotic myomectomy with experience in fertility-preserving treatment. Straightforward cases can also be treated in Kenya when an appropriately experienced myomectomy surgeon is available.
- Surgeon selection is given greater importance than hospital selection. The page 3 chart assigns 54% to surgeon factors and 46% to hospital factors, with genuine assessment of myomectomy before hysterectomy receiving 18%, followed by personal annual laparoscopic or robotic myomectomy volume at 16%.
- Hospital selection should include a dedicated minimally invasive gynaecology programme, experience with multiple or complex fibroids, structured post-operative and fertility follow-up, and appropriate accreditation. The guide also cautions that JCI/NABH accreditation is useful for safety and infection control but does not by itself prove specialist expertise in minimally invasive gynaecology.
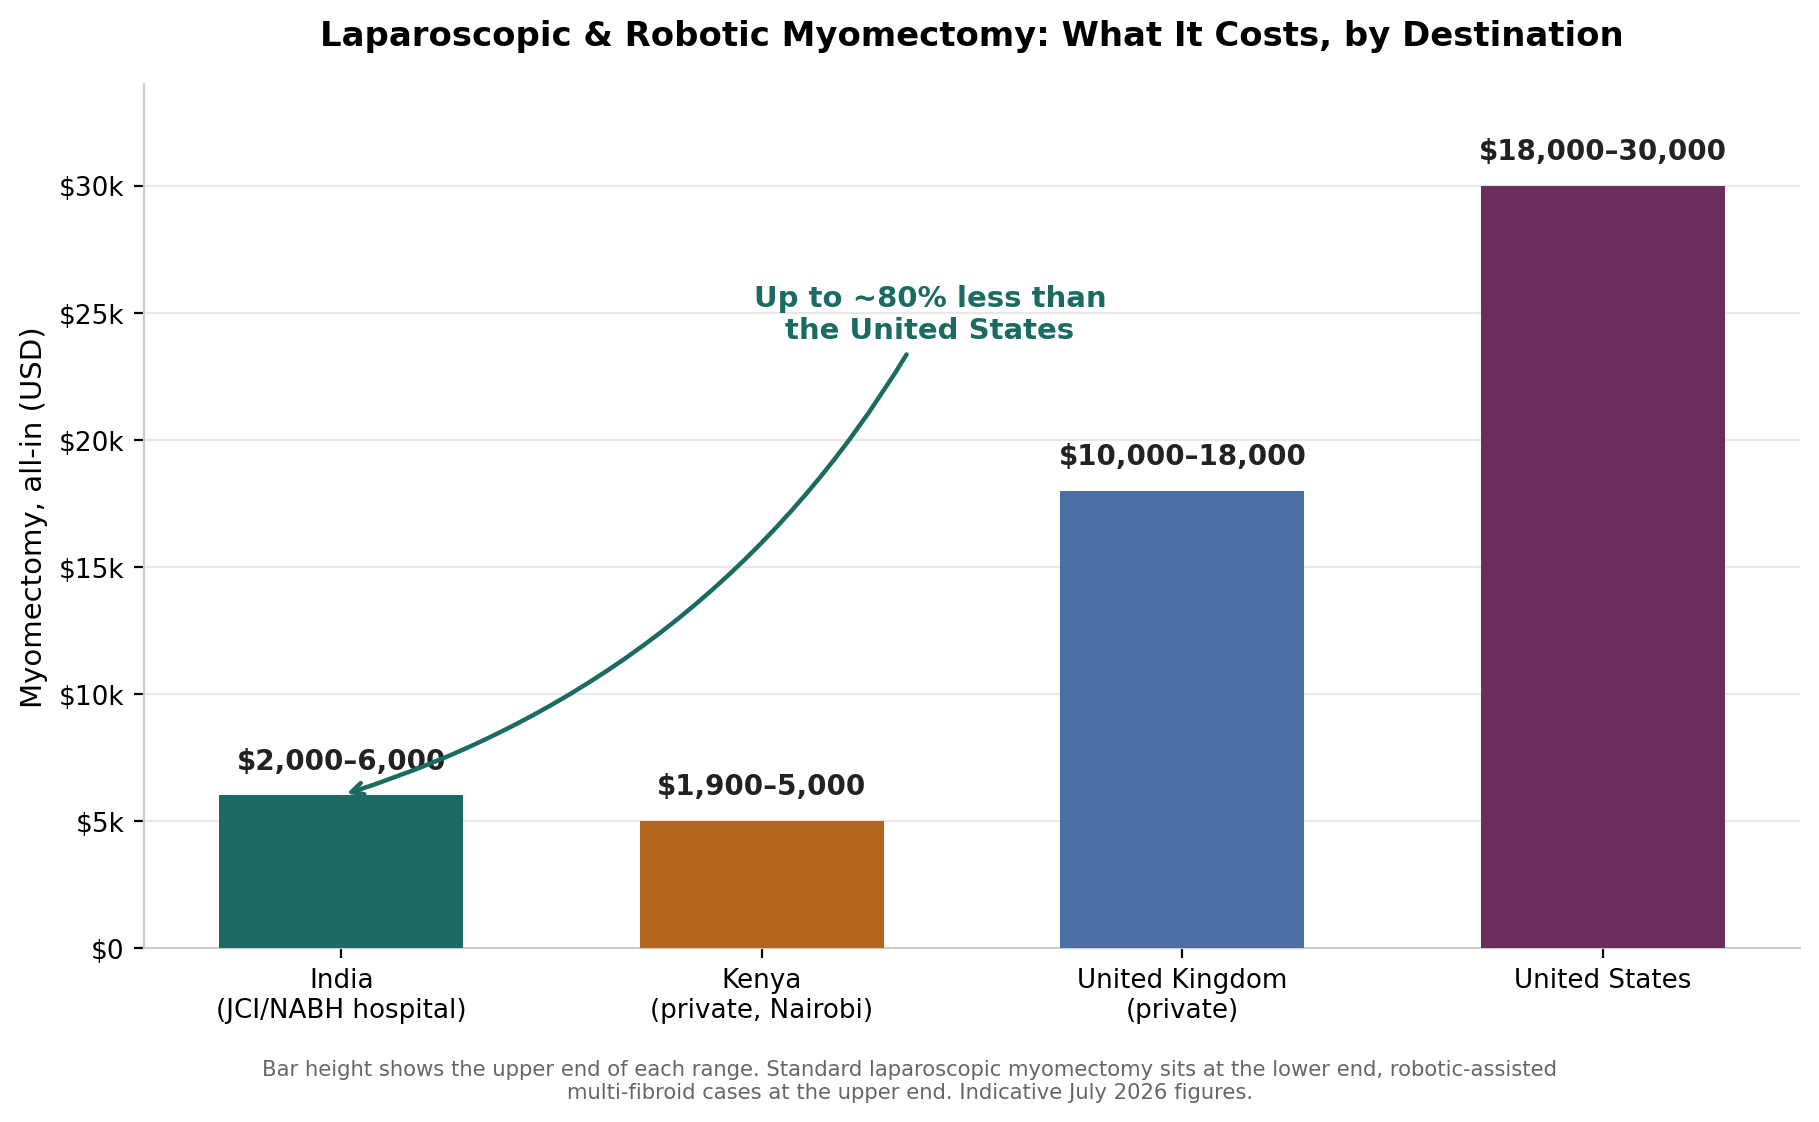
- The cost chart on page 4 gives an indicative range of US$2,000–6,000 in India, compared with US$1,900–5,000 in Kenya, US$10,000–18,000 in the UK and US$18,000–30,000 in the US. Patients should specifically confirm whether the quotation covers laparoscopic or robotic surgery and what happens financially if conversion to open surgery becomes necessary.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years of Experience
- Treatment
- Myomectomy for Uterine Fibroids
- Patients
- Kenyan Women Seeking Fertility-Preserving Treatment
- Key Specialist
- Minimally Invasive Gynaecological Surgeon
- Main Assessment
- Fibroid size, number, location and fertility goals
- Key Priority
- Assess myomectomy before defaulting to hysterectomy
- Surgical Options
- Laparoscopic, robotic and open myomectomy
- Key Selection Factor
- Personal annual laparoscopic/robotic myomectomy volume
- Complex Cases
- Multiple or large fibroids require specific surgical experience
- Hospital Requirement
- Dedicated minimally invasive gynaecology programme
- India Cost
- Approximately US$2,000–6,000
- Kenya Cost
- Approximately US$1,900–5,000
- UK Cost
- Approximately US$10,000–18,000
- US Cost
- Approximately US$18,000–30,000
- Quality Check
- JCI/NABH accreditation
- Pre-Travel Records
- Full MRI/ultrasound imaging and fertility goals
- Follow-Up
- Written recovery and fertility plan with Kenyan gynaecologist
- Key Warning Signs
- Hysterectomy recommended without a specific fibroid-based explanation
- Decision Principle
- Choose the least invasive fertility-preserving option that is medically appropriate
In Brief
For Kenyan women who want to preserve fertility while treating fibroids, the guide recommends asking whether myomectomy is genuinely possible before accepting hysterectomy. Surgeon-specific experience in laparoscopic or robotic myomectomy, particularly for complex or multiple fibroids, should be carefully assessed. The guide gives an indicative cost of US$2,000–6,000 in India and recommends confirming the surgical approach, conversion-to-open policy and fertility follow-up before booking.
Before the surgeon: the default treatment is often more than the problem requires
A study of women admitted to the gynaecology ward at a major Kenyan teaching and referral hospital found that total abdominal hysterectomy, removal of the entire uterus, was the single most common treatment for fibroids, used in 42% of cases. Myomectomy, which removes the fibroids while preserving the uterus and future fertility, was used in only 27%. Strikingly, the same study found fibroid prevalence was highest among nulliparous women, those who had never given birth, aged 35 to 39, precisely the group for whom preserving fertility matters most.
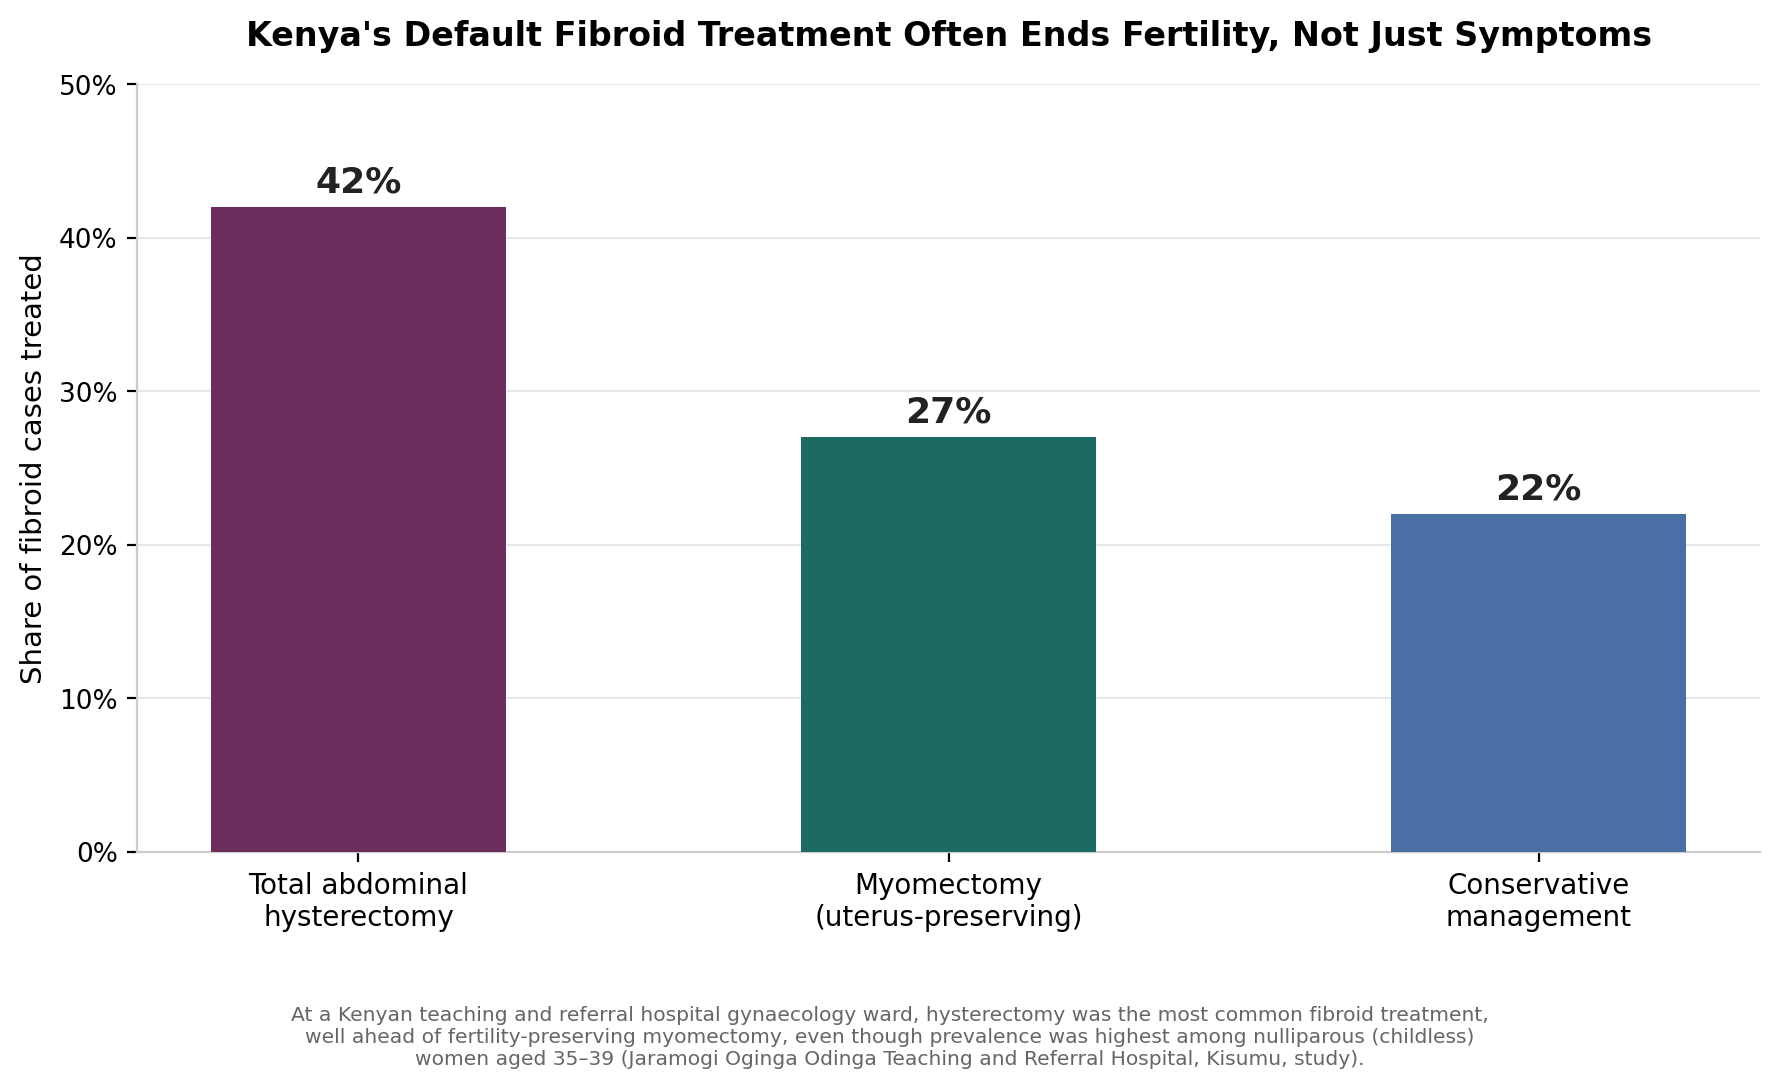
This pattern isn't unique to one hospital, and it isn't necessarily a sign of poor care. Hysterectomy is a genuinely reasonable choice when fertility isn't a goal, and it can be technically simpler than a careful, fertility-preserving myomectomy, particularly for large or numerous fibroids. But that same technical difficulty is exactly why myomectomy, especially laparoscopic or robotic myomectomy, requires a surgeon with real, specific experience in the technique, and why it deserves to be genuinely offered and discussed, not bypassed in favour of the more familiar operation.
The practical takeaway is to ask directly, before agreeing to any fibroid surgery, whether myomectomy is a realistic option for your case, and if hysterectomy is being recommended instead, exactly why, given your own fertility goals.
Should you travel at all?
Kenya's gynaecology units, including at Aga Khan University Hospital Nairobi and The Nairobi Hospital, perform both myomectomy and hysterectomy competently, and for straightforward cases where a surgeon with genuine myomectomy experience is available and fertility preservation isn't compromised, treatment in Kenya is a reasonable option.
For complex, multiple, or large fibroids, cases where a fertility-preserving approach is medically harder to achieve, and for genuine laparoscopic or robotic access, India is where I steer patients, confidently. India's high-volume minimally invasive gynaecology centres perform fertility-preserving myomectomy, including for complex multi- fibroid cases, as a routine, specifically requested procedure, with the laparoscopic and robotic volume needed to make even difficult cases uterus-preserving whenever medically possible.
Part one: judging the surgeon
1. Genuinely assesses myomectomy before defaulting to hysterectomy
I weight this above every other factor, and the chart below reflects that. Ask the surgeon directly whether myomectomy is a genuine option for your case, and if not, why not, referencing your specific fibroids, not a general preference for one procedure over the other.
2. Personal annual volume in laparoscopic or robotic myomectomy specifically
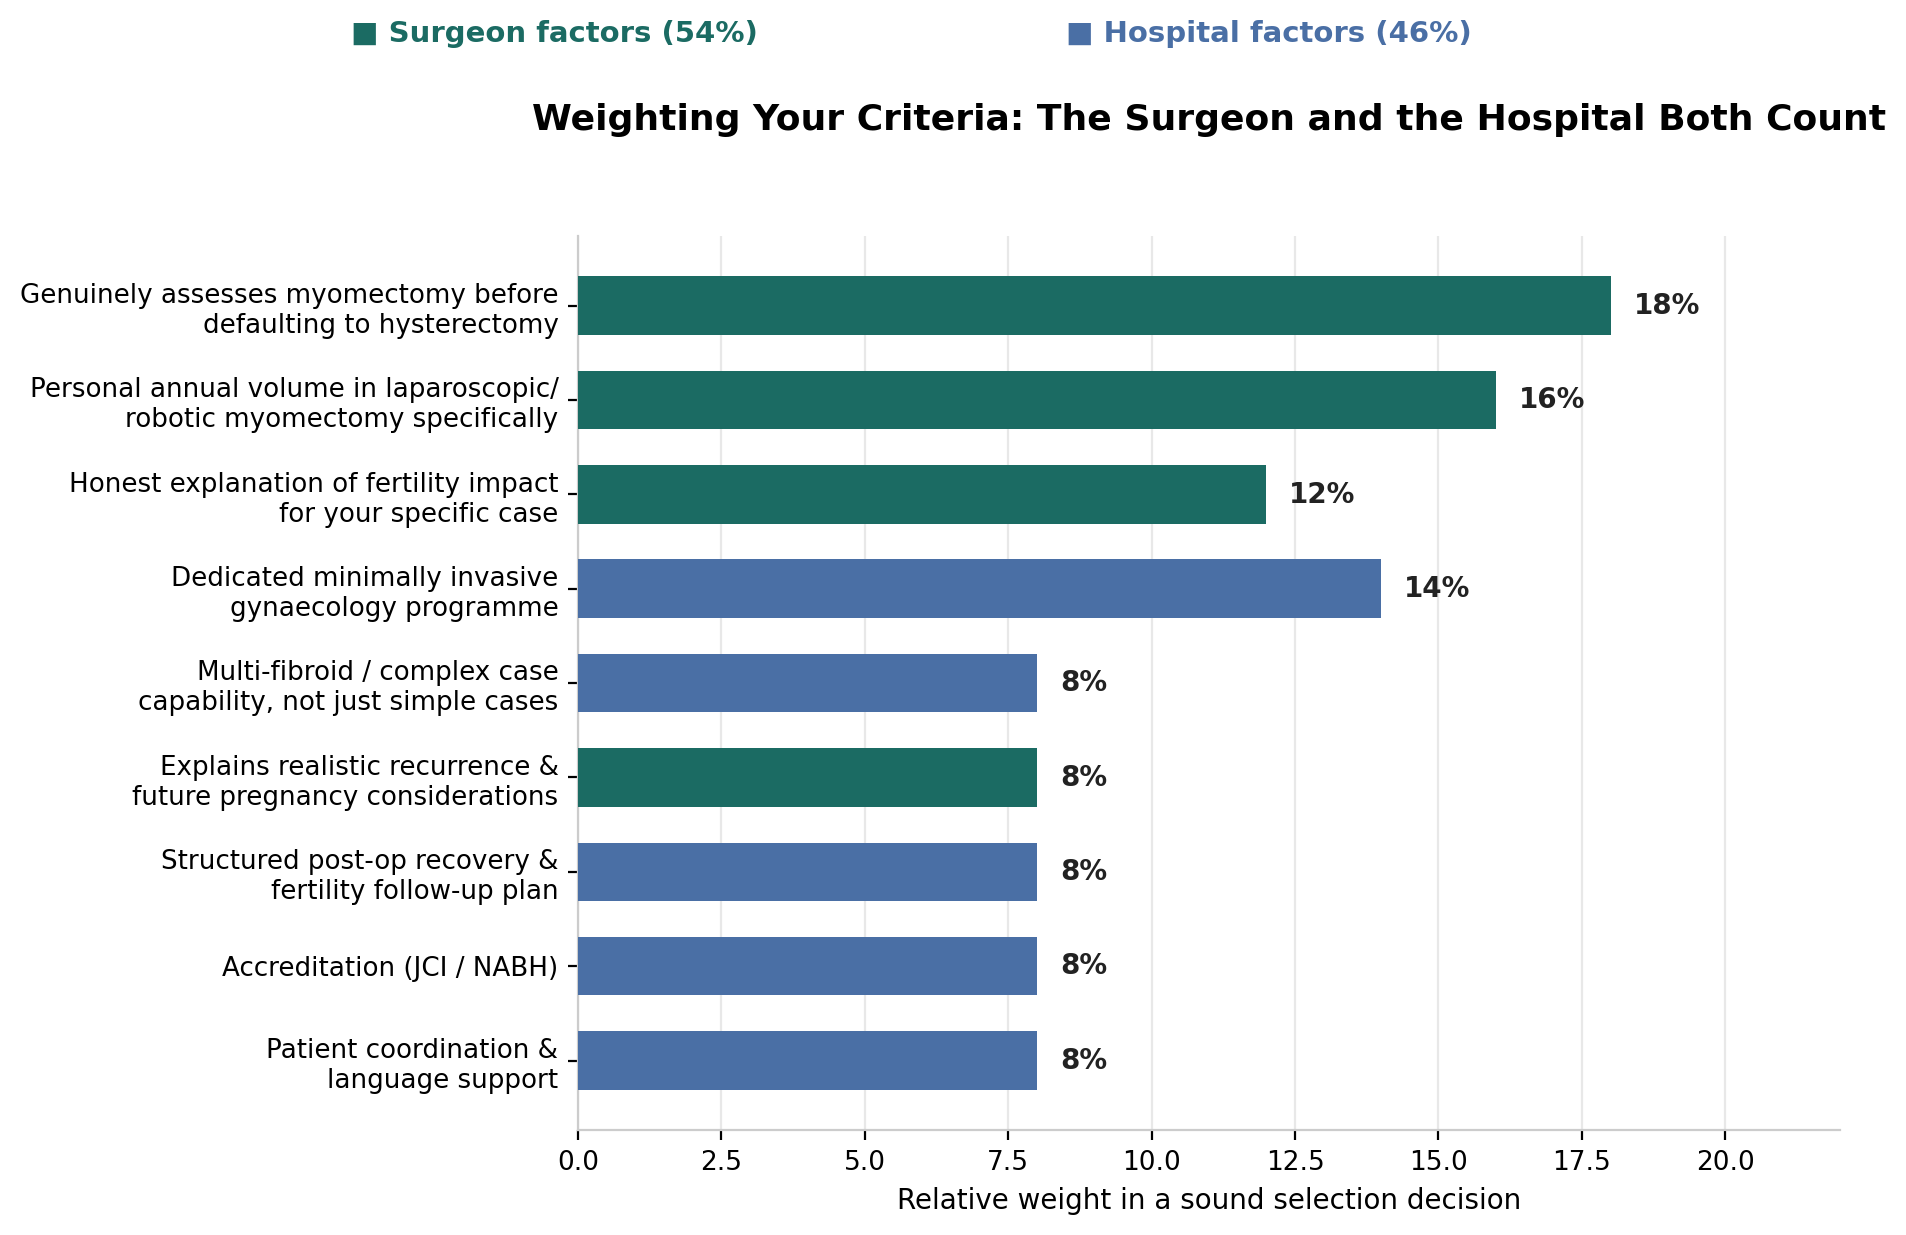
Ask how many laparoscopic or robotic myomectomies, not myomectomy in general or hysterectomy, the surgeon performs each year. This is a distinct technical skill from open surgery.
3. An honest explanation of fertility impact for your specific case
Ask what myomectomy would mean for your future fertility and pregnancy specifically, including any realistic risks, rather than a general reassurance that fertility will be preserved.
4. Explains realistic recurrence and future pregnancy considerations
Ask about your realistic risk of fibroids recurring, and what a future pregnancy would look like after your specific procedure, including any recommendations around delivery method.
Part two: judging the hospital
For myomectomy, the surgeon's specific technique experience carries more weight than the institution, reflected in the balance above, but the hospital still shapes whether a genuinely fertility-preserving option is available at all.
5. A dedicated minimally invasive gynaecology programme
Ask whether the hospital has a specific minimally invasive or robotic gynaecology programme, rather than laparoscopic myomectomy being one occasional option among many performed by a general gynaecology department.
6. Multi-fibroid or complex case capability
If you have multiple or large fibroids, ask specifically about the hospital's experience with complex cases, since not every centre confident with a single fibroid can safely manage a multi-fibroid, fertility-preserving case laparoscopically.
7. A structured post-operative recovery and fertility follow-up plan
Ask what recovery looks like, and whether there's a structured plan for follow-up imaging and fertility guidance once you're home.
8. Accreditation, read properly
JCI and NABH accreditation are meaningful filters on safety and infection control, but say nothing about minimally invasive gynaecology sub-specialisation specifically. Use accreditation to exclude weak candidates, not to choose
between the strong ones.
9. The cost you will actually pay
Let me be emphatic about this, because 24 years of handling these cases has taught me nothing more consistently: disputes almost never concern the quoted price. They concern what the quote silently omitted. For myomectomy specifically, insist the estimate states whether the price assumes laparoscopic or robotic access, and what happens if the surgeon needs to convert to open surgery during the procedure.
Budget beyond the surgery. Direct Nairobi–Delhi and Nairobi–Mumbai flights run roughly 550 to 850 dollars return, and the shorter recovery time for laparoscopic or robotic myomectomy generally keeps accommodation costs modest compared to open surgery.
Four signals that should make you pause
Certain patterns reliably precede a difficult outcome. A surgeon who recommends hysterectomy without a specific, fibroid-based explanation of why myomectomy isn't possible. No clear personal volume figure in laparoscopic or robotic myomectomy specifically. A quote that doesn't distinguish laparoscopic, robotic, and open pricing. And a hospital unable to describe its experience with multi-fibroid or complex cases.
None alone proves a bad hospital. Together they warrant a second opinion before you commit to surgery.
The Kenya-specific practicalities
Send the full imaging, MRI or ultrasound, not just a written report, along with a clear statement of your fertility
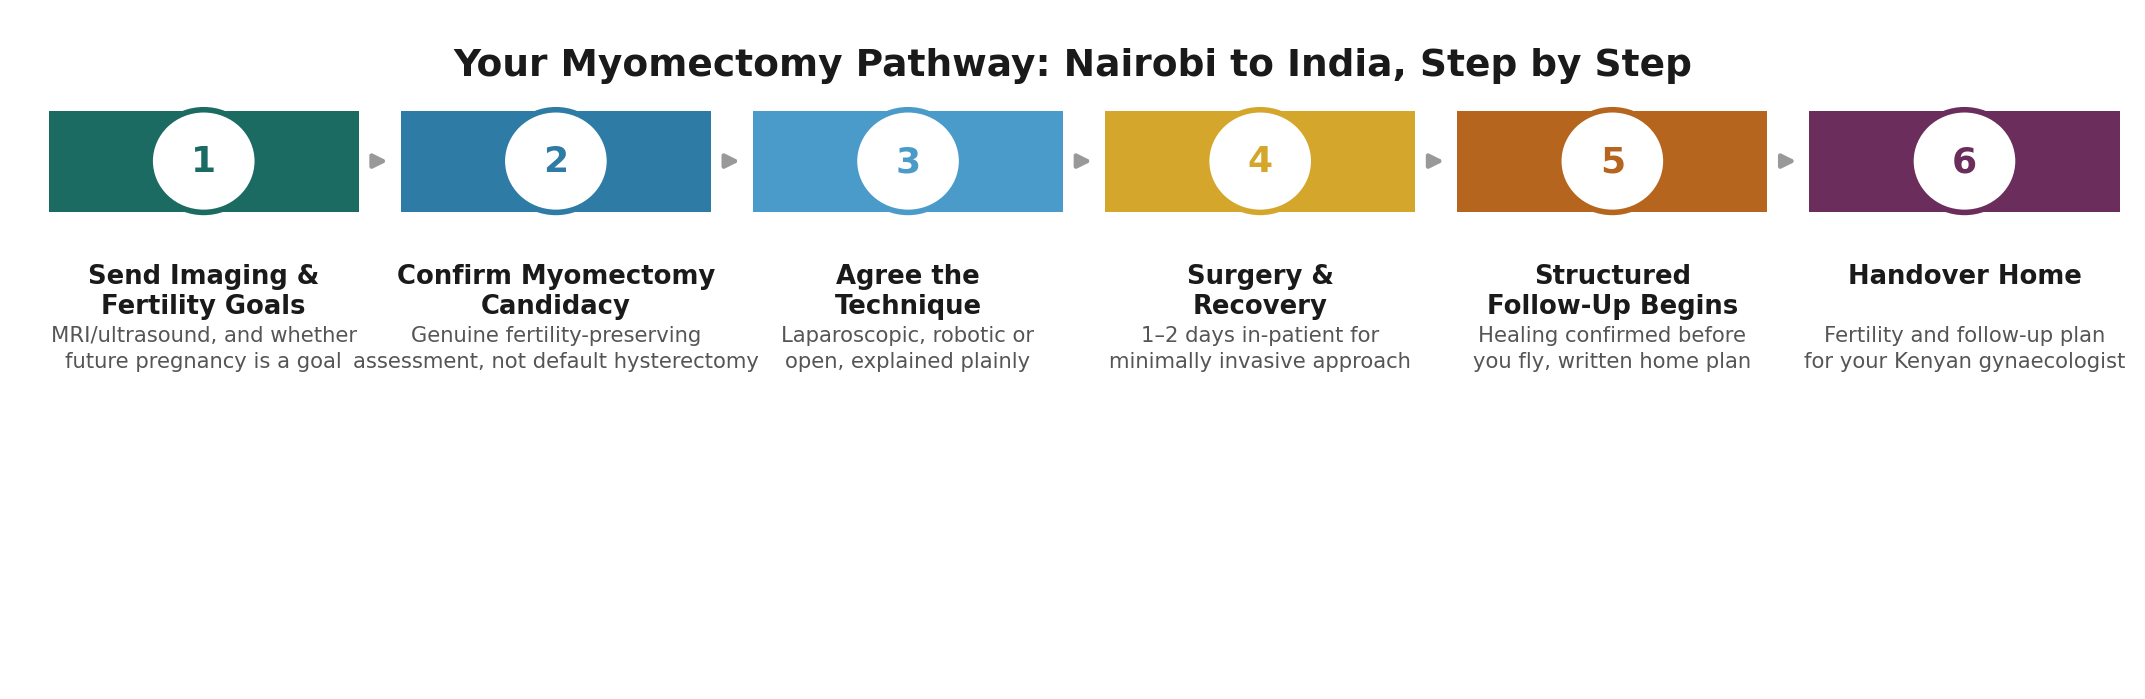
goals, so the surgical team can assess genuine myomectomy candidacy before you arrive.
Direct Nairobi–Delhi and Nairobi–Mumbai flights make this roughly a six-hour journey. The Indian medical e-visa is issued within three to five working days against a hospital letter, and an attendant can travel with you on a medical attendant visa.
Agree in advance on a written recovery and fertility follow-up plan your Kenyan gynaecologist can continue once you are home.
The questions I would ask before paying a deposit
Of the surgeon:
- Is myomectomy a genuine option for my case, and if not, why not?
- How many laparoscopic or robotic myomectomies do you personally perform each year?
- What would this mean for my future fertility and pregnancy specifically?
- What is my realistic risk of fibroid recurrence?
Of the hospital:
- Do you have a dedicated minimally invasive gynaecology programme?
- What is your experience with multi-fibroid or complex cases?
- What does my recovery and follow-up plan look like?
- What exactly is excluded from the quoted price?
- May I speak to a previous East African patient treated for a similar case?
A team that answers all nine without irritation is very likely the right team. One that turns vague at the first or second has told you what you needed to know at no cost at all.
Straight Answers for Kenyan Patients about Myomectomy Surgeons and Hospitals in India
How do I choose the best surgeon in India for myomectomy as a Kenyan patient?
Ask his annual volume in laparoscopic or robotic myomectomy specifically, and ask him to explain, based on your own imaging, whether myomectomy is realistic for your fibroids before hysterectomy is even mentioned.
How much does myomectomy cost in India for a Kenyan patient?
Typically 2,000 to 6,000 US dollars all in. The same surgery runs roughly 1,900 to 5,000 dollars in Kenya, 10,000 to 18,000 in the UK, and 18,000 to 30,000 in the US.
Why is hysterectomy so often chosen over myomectomy for fibroids in Kenya?
Partly because hysterectomy can be technically simpler, especially for large or multiple fibroids, and partly because fertility-preserving myomectomy demands more specific surgical skill. A Kenyan study found hysterectomy was used in 42% of fibroid cases versus 27% for myomectomy, even though fibroid prevalence was highest among childless women in their late thirties.
Will myomectomy affect my chances of getting pregnant?
For most women, myomectomy is intended to preserve or improve fertility, but the specific impact depends on the number, size, and location of your fibroids. Ask your surgeon for a case-specific answer rather than a general reassurance.
What's the difference between laparoscopic and robotic myomectomy?
Both are minimally invasive, using small incisions rather than open surgery. Robotic myomectomy uses a surgeon- controlled robotic system for additional precision and dexterity, particularly useful for complex or multiple fibroids, while laparoscopic myomectomy uses handheld instruments through a camera-guided approach.
Can fibroids come back after myomectomy?
Yes, new fibroids can develop over time, since myomectomy removes existing fibroids but doesn't change the underlying tendency to form them. Ask your surgeon about your specific recurrence risk based on your fibroid pattern and age.
A closing word
For a Kenyan woman who wants her fibroids treated without her fertility being an afterthought, India offers what a genuinely fertility-preserving option requires: surgeons with deep laparoscopic and robotic myomectomy experience, and hospitals built to make even complex, multi-fibroid cases uterus-preserving whenever medically possible, at a fraction of UK or US cost. The best surgeon is the one who assesses myomectomy honestly before ever mentioning hysterectomy. The best hospital pairs him with genuine minimally invasive capability and a recovery plan built around your future, not just your symptoms. If you would like me to look at your imaging and talk through honestly whether myomectomy is realistic for you, send it across.
Sources
- 🌐 Prevalence and Management of Uterine Fibroids among Women of Reproductive Age at Jaramogi Oginga Odinga Teaching and Referral Hospital
- 🌐 Epidemiology of uterine fibroid in black African women: a systematic scoping review. PMC
- 🌐 Global epidemiological characteristics of uterine fibroids. Archives of Medical Science, 2023
- 🌐 National Medical Commission of India — surgeon and specialist registration verification
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH) — accredited hospital directory
- 🌐 Kenya Social Health Authority (SHA) — benefits packages and overseas treatment guidance
Frequently Asked Questions by Kenyans about Myomectomy Surgeons and Hospitals in India
Why should myomectomy be considered before hysterectomy?
Myomectomy removes fibroids while preserving the uterus. For women who still want children, the guide recommends confirming whether myomectomy is a realistic option before accepting hysterectomy.
How common are fibroids among African women?
The guide states that more than 80% of African women may develop fibroids by age 50, with fibroids occurring at roughly two to three times the rate seen in white women.
What does the Kenyan study say about fibroid treatment?
The cited study found that 42% of fibroid cases were treated with total abdominal hysterectomy, while 27% underwent myomectomy.
When might India be useful for a Kenyan patient?
India may be particularly relevant for large, multiple or complex fibroids and when genuine laparoscopic or robotic fertility-preserving surgery is difficult to access locally.
How should I choose a myomectomy surgeon in India?
Ask how many laparoscopic or robotic myomectomies the surgeon personally performs each year, rather than relying on general gynaecological surgery experience.
Will myomectomy preserve my fertility?
Myomectomy is intended to preserve the uterus, but the impact on future fertility depends on the number, size and location of the fibroids and the surgical approach. A case-specific assessment is essential.
Can fibroids return after myomectomy?
Yes. Myomectomy removes existing fibroids but does not eliminate the underlying tendency to develop new fibroids. The surgeon should explain the patient's individual recurrence risk.
What is the difference between laparoscopic and robotic myomectomy?
Both use minimally invasive access through small incisions. Robotic surgery uses a surgeon-controlled robotic system that can provide additional dexterity and precision, which may be useful in selected complex cases.
How much does myomectomy cost in India?
The guide gives an indicative range of US$2,000–6,000. Patients should confirm whether the quotation is for laparoscopic, robotic or open surgery and what happens if conversion to open surgery is required.
What should Kenyan patients send before travelling?
Send the complete MRI or ultrasound imaging and a clear statement of fertility goals so the Indian surgical team can assess myomectomy candidacy before arrival.
Page Summary
This seven-page Kenya patient guide explains how women can evaluate myomectomy surgeons and hospitals in India, particularly when fertility preservation is important. It compares hysterectomy and myomectomy in the Kenyan context, highlights laparoscopic and robotic options for complex fibroids, provides a 54% surgeon / 46% hospital weighting, compares indicative costs across India, Kenya, the UK and US, and outlines the pathway from sending imaging and fertility goals through candidacy assessment, surgery, recovery and follow-up with a Kenyan gynaecologist.
Citation Block
| Topic | Information |
|---|---|
| Topic | Myomectomy in India for Kenyan Patients |
| Treatment | Laparoscopic, Robotic & Open Myomectomy |
| Patients | Kenyan Women Seeking Fertility Preservation |
| Specialist | Minimally Invasive Gynaecological Surgeon |
| Main Assessment | Fibroid size, number, location and fertility goals |
| Key Priority | Assess myomectomy before hysterectomy |
| Surgeon Check | Annual laparoscopic/robotic myomectomy volume |
| Fertility Discussion | Case-specific pregnancy and fertility implications |
| Complex Cases | Experience with multiple and large fibroids |
| Hospital Check | Dedicated minimally invasive gynaecology programme |
| Follow-Up | Recovery and fertility monitoring plan |
| India Cost | Approximately US$2,000–6,000 |
| Kenya Cost | Approximately US$1,900–5,000 |
| UK Cost | Approximately US$10,000–18,000 |
| US Cost | Approximately US$18,000–30,000 |
| Quote Check | Surgical approach and conversion-to-open costs |
| Pre-Travel Records | MRI/ultrasound and fertility goals |
| Quality Check | JCI/NABH accreditation |
| Warning Signs | Hysterectomy without a specific fibroid-based explanation |
| Selection Weighting | 54% surgeon factors and 46% hospital factors |
| Key Statistic | Hysterectomy 42% vs myomectomy 27% in the cited Kenyan study |
| Patient Pathway | Imaging → candidacy → technique → surgery/recovery → follow-up |
| Decision Principle | Preserve fertility when medically appropriate |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Kenya










Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Kenya who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Ethiopia
- Somalia
- Tanzania
- Uganda
- Seychelles
- Guinea
- Guinea-Bissau
- Liberia
- Mali
- Mauritania
- Niger
- Nigeria
- Senegal
- Togo
- South Sudan
- Sierra Leone
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Kenya to India: Your Complete Patient Support Guide
- Brain Tumour Surgery in India for Kenyan Patients
- Cancer Treatment and Surgery in India for Kenyan Patients
- Cardiac Treatment and Surgery in India for Kenyan Patients
- Heart Valve Replacement Surgery in India for Kenyan Patients
- Knee Replacement in India for Kenyan Patients
- Prostate Cancer Treatment and Surgery in India for Kenyan Patients
- Spine Treatment and Surgery in India for Kenyan Patients
- Selecting the Best Bariatric Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Cancer Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Cardiac Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Dental Surgeons and Clinics in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Hip Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Kidney Transplant Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Knee Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Liver Transplant Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Neurosurgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Prostate Cancer Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For
- Selecting the Best Spine Surgeons and Hospitals in India: What Kenyan Patients Should Actually Look For