

Selecting the Best Bone Marrow Transplant Specialists and Teams in India — A Somali Patient's Guide
A bone marrow transplant is weeks of inpatient care, not a single procedure — the laboratory, the isolation unit, and the blood bank behind the physician matter as much as the physician's own skill. This guide sets out how to verify both.
Few procedures in this guide series depend as heavily on the team behind the named physician as a bone marrow transplant. Only around 30% of patients have a fully HLA-matched sibling donor within the family, and even then the outcome still turns on high-resolution typing, a dedicated isolation unit, and a blood bank that can supply irradiated, leukocyte-depleted products on demand. In 24 years of guiding patients through transplant decisions, I have seen good physicians let down by thin supporting infrastructure more often than the reverse. This guide sets out, plainly, how a Somali patient should verify both before committing to travel.
Healing Journeys of Somali Patients



Key Takeaways
- The guide explains that bone marrow transplant is a prolonged inpatient treatment, with donor selection being one of the earliest decisions. Only around 30% of patients have a fully HLA-matched sibling donor, making early HLA testing, donor assessment, dedicated isolation facilities and reliable blood-bank support important.
- Before choosing a transplant programme, Somali patients should determine the appropriate donor option—matched sibling, matched unrelated or haploidentical donor—based on the patient's diagnosis and available HLA results. The guide recommends discussing how the donor source affects conditioning, risks and recovery.
- For physician selection, priority should be given to a named BMT physician with dedicated transplant fellowship training, recent experience with the exact transplant type and the ability to clearly explain donor selection and conditioning.
- The page 2 weighting graphic gives 44% to the physician and 56% to the transplant programme. Page 3 ranks dedicated BMT fellowship training highest, followed by 6-loci HLA typing and exact transplant-type case volume.
- Important programme checks include a HEPA-filtered BMT unit, transplant-specific accreditation, high-resolution HLA typing and an in-house blood bank providing irradiated and leukocyte-depleted blood products. A structured GVHD follow-up plan through at least day 100 should also be confirmed.
- The guide warns that initial transplant quotations may exclude isolation, monitoring or GVHD-related costs. Somali patients should obtain a complete written estimate, start family HLA testing early and send their diagnosis and HLA results to centres before travelling.
- Travel planning should be arranged after treatment confirmation. The guide notes that Somali patients apply through Nairobi or Addis Ababa, and that there is no direct Mogadishu–India flight, making advance visa and connecting-flight planning necessary.
Quick Facts
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
- Treatment
- Bone Marrow / Stem Cell Transplant
- Patients
- Somali Patients
- First Assessment
- Diagnosis and family HLA results
- Key Specialist
- Bone Marrow / Stem Cell Transplant Physician
- Decision Weighting
- Physician 44% / Programme 56%
- Training Check
- Dedicated BMT fellowship
- Donor Options
- Matched sibling, matched unrelated or haploidentical donor
- Case Volume
- Exact transplant type in last 12 months
- HLA Testing
- High-resolution 6-loci typing
- Isolation
- Dedicated HEPA-filtered BMT unit
- Accreditation
- JACIE / FACT / equivalent
- Blood Bank
- Irradiated and leukocyte-depleted blood products
- Conditioning
- Individualised donor and conditioning explanation
- Follow-Up
- GVHD monitoring through at least day 100
- Cost Check
- Written estimate through day-100 monitoring
- Cost Risk
- Isolation and GVHD readmission may add costs
- Budget
- 20–25% margin
- Medical Records
- Diagnosis and HLA results
- Family Testing
- Early HLA typing of siblings
- Visa
- Longer-duration medical visa
- Visa Route
- Nairobi or Addis Ababa
- Travel
- Connecting flights from Mogadishu
- Communication
- Somali- or Arabic-speaking coordinator
- Home Follow-Up
- Remote GVHD monitoring plan
- Key Warning
- Low-resolution or unverified HLA typing
- Decision Principle
- Prioritise transplant-specific programme infrastructure alongside physician expertise.
This is not a case against transplant travel itself. India remains a genuine option for Somali patients with thalassemia, sickle cell disease, aplastic anaemia, leukaemia, and lymphoma precisely because it combines experienced physicians with programme-level infrastructure few nearby alternatives can match — provided both are confirmed in advance.
In Brief
For Somali patients considering bone marrow transplant in India, the key decision is to verify both a fellowship-trained transplant physician and a genuine transplant programme with high-resolution HLA typing, a dedicated HEPA-filtered isolation unit and reliable blood-bank support. Patients should establish the donor option early, understand the conditioning plan, obtain complete costs through day-100 monitoring and confirm a long-term GVHD follow-up pathway before travelling.
First, Establish What Your Case Actually Needs
Before comparing physicians or hospitals, get clarity on donor options — a matched sibling, a matched unrelated donor, or a haploidentical (half-matched) family donor — and how each affects conditioning, risk, and recovery time. This assessment should come from a genuine transplant physician reviewing your actual diagnosis and family HLA results, not a general estimate from a description alone.
Two Decisions, Not One
Choosing well depends on two things: the transplant physician's own dedicated training, and the programme's supporting infrastructure — its HLA lab, its isolation unit, its blood bank. Unlike most topics in this series, the programme carries the larger share here, because a transplant is weeks of inpatient care where infection control
and blood-product readiness shape the outcome as much as any single decision the physician makes.
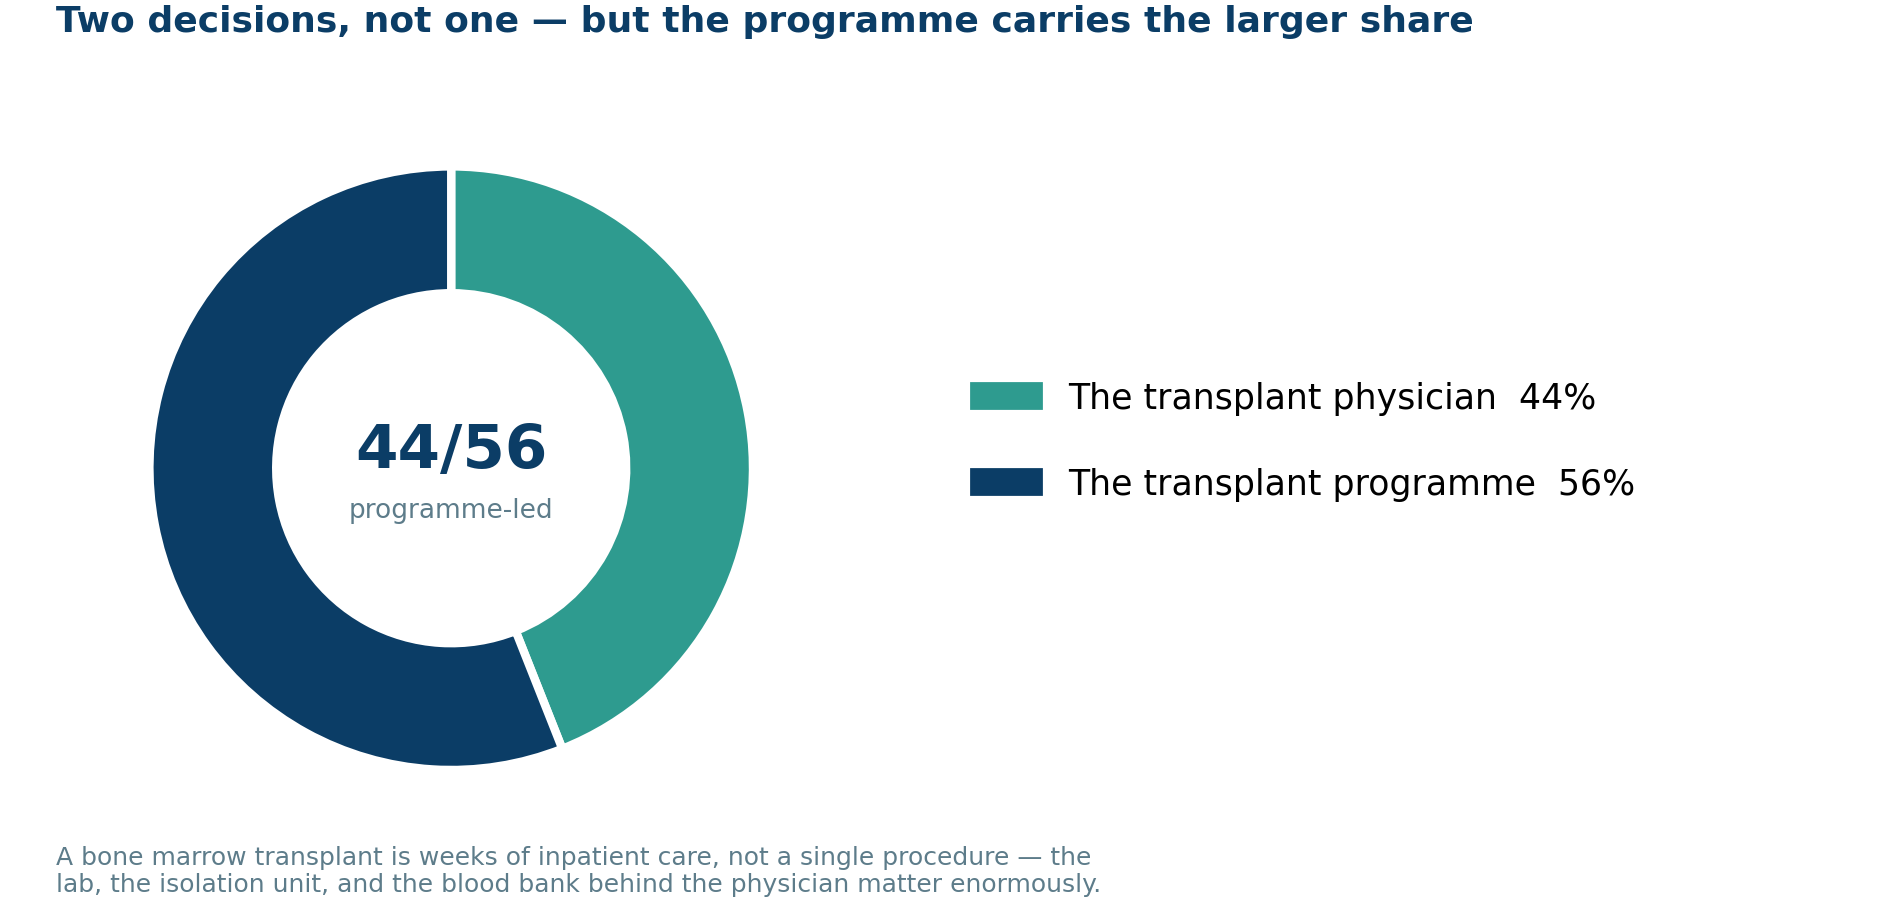
A bone marrow transplant is weeks of inpatient care, not a single procedure — the lab, the isolation unit, and the blood bank behind the physician matter enormously.
Part One: Verifying the Physician
These three points matter more than a hospital's overall reputation or general marketing claims.
1. A named physician with a dedicated transplant (BMT) fellowship — not a general haemato-oncologist who occasionally oversees a transplant.
2. Documented case volume in your exact transplant type, in the last 12 months — sibling-matched, unrelated-donor, and haploidentical transplants carry different risk profiles and need separate track records.
3. An honest explanation of donor source and conditioning regimen for your specific diagnosis, rather than a generic protocol applied to every case.
| Stage | What it means |
|---|---|
| MBBS | Basic medical degree — the entry point, not evidence of transplant-specific skill on its own. |
| MD / DM Clinical Haematology | The base postgraduate qualification — years of foundational training in blood disorders. |
| Fellowship in Bone Marrow / Stem Cell Transplant | Additional focused training in transplant medicine specifically — the credential that actually confirms the specialist skill this guide is asking you to verify. |
Ask for this exact credential chain — a general haematology qualification alone does not confirm transplant-specific training.
Part Two: Verifying the Programme
Once the physician is confirmed, the programme's own systems shape how safely weeks of isolation and recovery unfold.
4. High-resolution, 6-loci HLA typing confirmed for donor and recipient — lower-resolution typing can miss mismatches that carry real clinical consequence, even among siblings.
5. A dedicated, HEPA-filtered isolation or BMT unit, not a general oncology ward repurposed for transplant patients.
6. JACIE, FACT, or an equivalent transplant-specific accreditation — distinct from general hospital accreditation, and auditing the transplant programme itself.
7. An in-house blood bank that can reliably supply irradiated, leukocyte-depleted blood products, which measurably reduce graft-related complications.
8. A structured GVHD-monitoring and follow-up plan through at least the first 100 days, the window where transplant-related risk is highest.
9. A written, itemised cost estimate covering the full admission through day-100 monitoring, not just the transplant procedure itself.
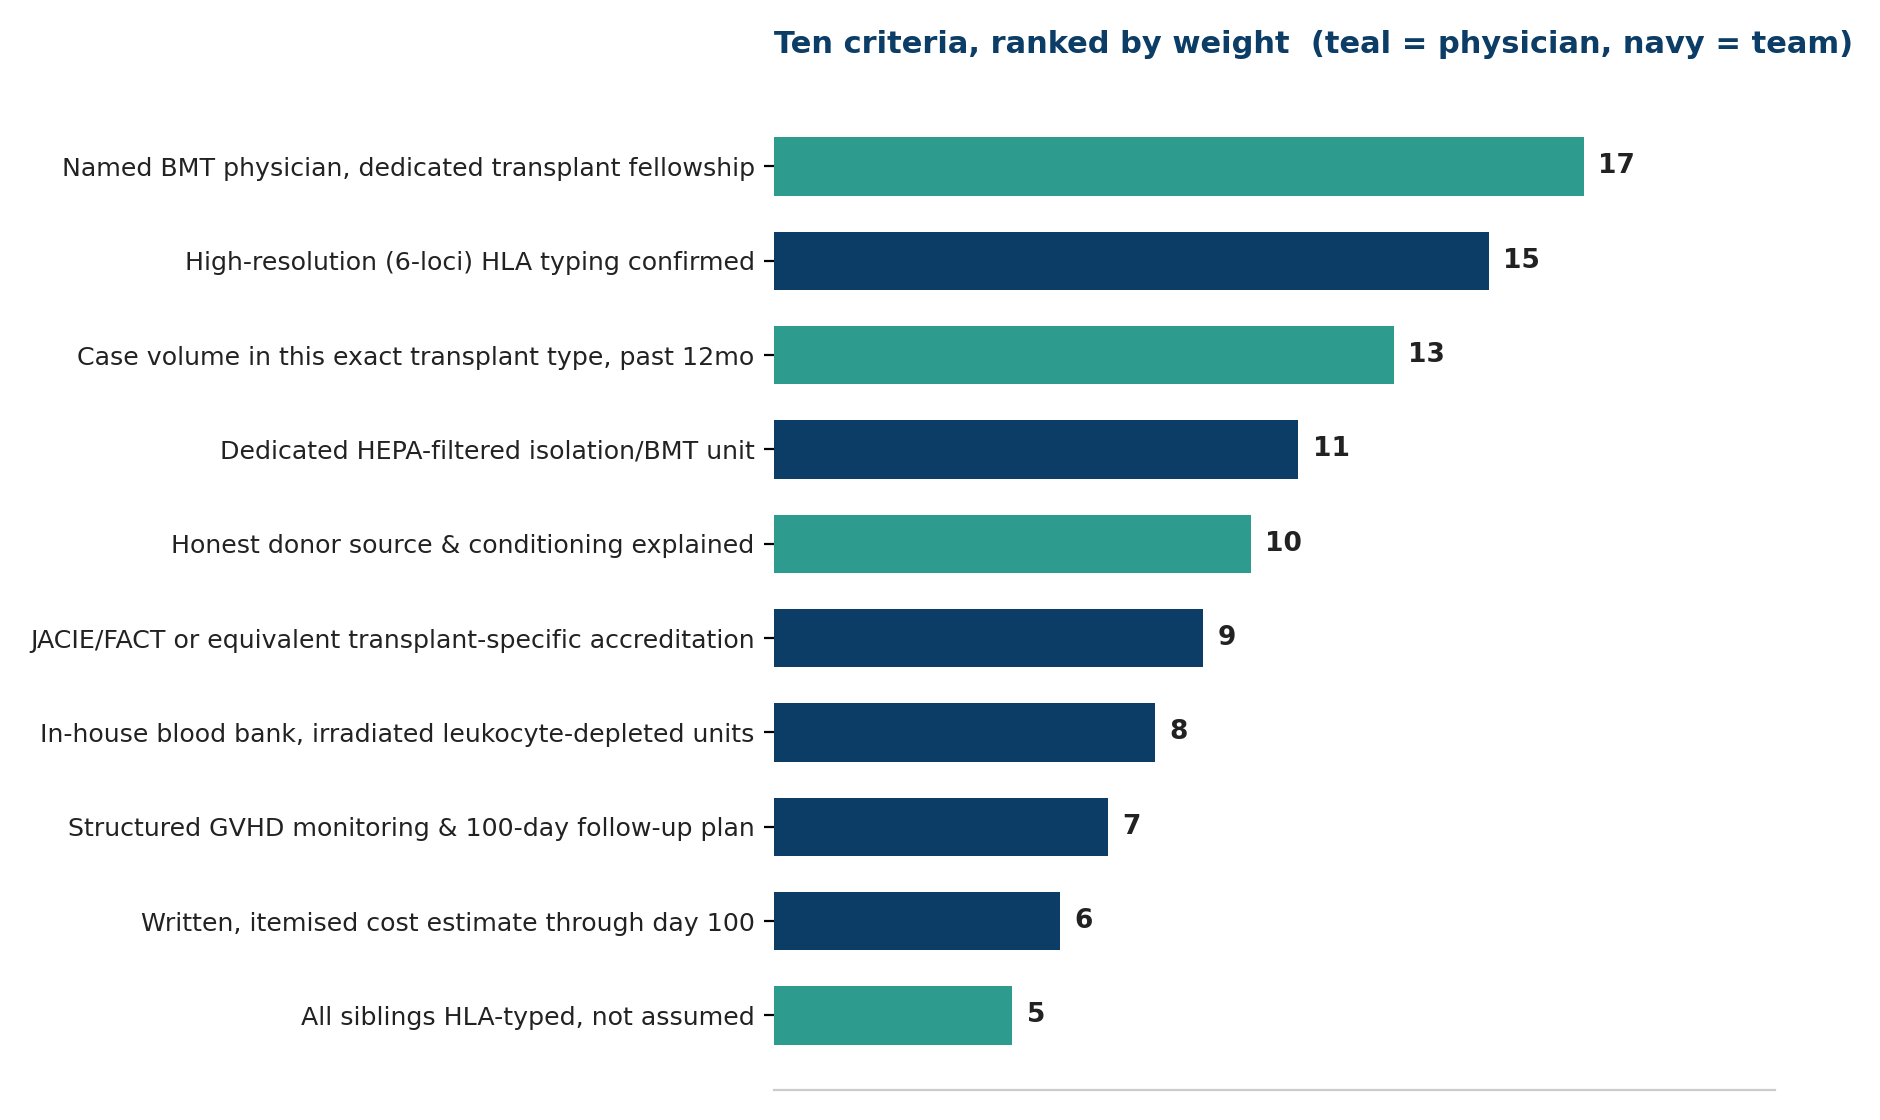
All ten criteria ranked by relative weight — HLA typing accuracy sits second only to the physician's own training.
| Verification check | Genuine transplant programme | General, unverified provider |
|---|---|---|
| Named physician, dedicated BMT fellowship | Yes | No |
| High-resolution (6-loci) HLA typing | Yes | No |
| Honest donor & conditioning explanation | Yes | Partly |
| Dedicated HEPA-filtered isolation unit | Yes | No |
| Written, itemised cost estimate through day 100 | Yes | Partly |
A simple check to run against any centre you are considering, before booking anything.
What the quote doesn't always show. In 24 years of reviewing these estimates, I have found disputes almost never concern the headline number — they concern what it silently left out: the isolation-room daily rate billed separately, or day-100 monitoring visits priced as though care ends at discharge. Get every line item in writing, including what a GVHD readmission would cost, before paying any deposit.
What a Somali Patient Should Weigh in Particular
Start family HLA typing early, not just for the patient but for all siblings — this is often the single longest lead-time item in the whole process, and delaying it delays everything after it.
Currency and budget. Somalia is heavily dollarised — hospital-scale payments are quoted and settled in US dollars, not the shilling (roughly 570 SOS/US$1 in mid-2026). Budget with a 20–25% margin above the written estimate, given the length of stay.
Visa timing. India has no resident mission in Mogadishu, so Somali passport holders apply through the Indian High Commission in Nairobi or the Embassy of India in Addis Ababa, with a no-objection letter from the Somali embassy there. Transplants typically need a longer-duration visa than most procedures here.
No direct flight. Ethiopian Airlines via Addis Ababa is the most frequent route from Mogadishu; flydubai, Emirates, and Qatar Airways offer alternatives via Dubai or Doha.
A Somali- or Arabic-speaking coordinator, and a clear plan for who manages months of GVHD monitoring once home — transplant follow-up capacity within Somalia remains essentially absent, so confirm the programme's remote process before travel, not after.
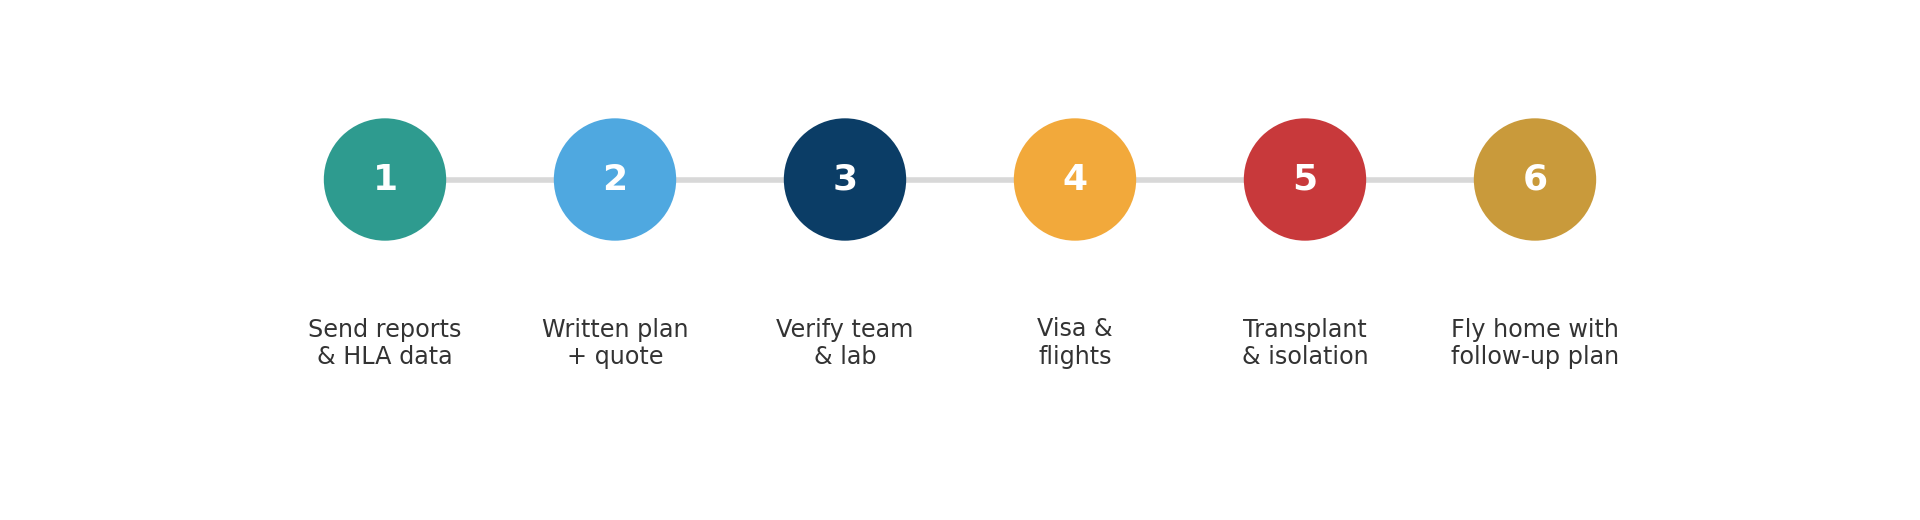
The practical sequence once you have chosen and verified your physician and programme.
Four Signals That Should Make You Pause
1. No clear confirmation of dedicated BMT fellowship training.
2. HLA typing done only at low resolution, or not independently verified.
3. No dedicated isolation unit — patients housed on a general ward.
4. Pressure to pay the full balance before a written transplant plan exists.
Questions Worth Asking Directly
| Ask the physician | Ask the programme |
|---|---|
| Are you fellowship-trained specifically in BMT? | Is HLA typing done to 6-loci resolution, in-house? |
| How many transplants like mine have you done this year? | Do you hold JACIE, FACT, or equivalent accreditation? |
| Why this donor source and conditioning for my case? | What does day-100 follow-up actually involve? |
A Closing Word
A bone marrow transplant is weeks of inpatient care built on infrastructure most families never see until they need it, which is why the programme behind the physician matters as much as the physician performing it. A named, fellowship-trained specialist, backed by high-resolution HLA typing and a dedicated isolation unit, is the baseline worth insisting on before any deposit is paid — and no genuine programme will hesitate to confirm this clearly. If you can share your diagnosis and any HLA results already available, I am glad to review them honestly.
Sources
- 🌐 National Medical Commission of India — verify any physician's registration — nmc.org.in
- 🌐 National Accreditation Board for Hospitals & Healthcare Providers (NABH) — nabh.co
- 🌐 High Commission of India, Nairobi — visa services for Somali nationals — hcinairobi.gov.in
- 🌐 Embassy of India, Addis Ababa — medical visa requirements — indianembassy.gov.et
- 🌐 JACIE / FACT accreditation standards for haematopoietic cell transplantation — jacie.org
Frequently Asked Questions by Somalis about Bone Marrow Transplant Specialists and Teams in India
Why is the transplant programme so important?
The guide gives 56% weighting to the transplant programme, because HLA testing, isolation, blood-bank support and follow-up are critical throughout the transplant pathway.
What donor options should Somali patients discuss?
The guide identifies matched sibling, matched unrelated and haploidentical family donors as important donor options to evaluate.
What type of transplant physician should patients choose?
Look for a named physician with dedicated BMT or stem-cell transplant fellowship training and recent experience with the exact transplant type.
Why is 6-loci HLA typing important?
The guide recommends high-resolution 6-loci HLA typing for donor and recipient, because lower-resolution testing may miss clinically important mismatches.
What type of isolation facility should be verified?
Patients should confirm a dedicated HEPA-filtered isolation or BMT unit, rather than a general oncology ward being used for transplant patients.
What blood-bank support is required?
The programme should have an in-house blood bank capable of reliably supplying irradiated and leukocyte-depleted blood products.
Why is accreditation important?
The guide recommends JACIE, FACT or an equivalent transplant-specific accreditation, which evaluates the transplant programme rather than only general hospital standards.
What should the cost estimate include?
The quotation should cover the full admission through at least day-100 monitoring, including potential additional costs such as isolation-room charges and GVHD readmission.
Why should family HLA testing start early?
The guide identifies family HLA testing as potentially one of the longest lead-time steps, so delaying sibling testing can delay the entire transplant pathway.
What are the main warning signs?
Be cautious if there is no dedicated BMT fellowship, only low-resolution or unverified HLA typing, no dedicated isolation unit or pressure to pay the full balance before a written transplant plan.
Page Summary
This five-page guide focuses on transplant physician expertise and programme-level infrastructure, with the programme receiving the larger 56% weighting compared with 44% for the physician. Page 1 explains why HLA matching, isolation facilities and blood-bank readiness are central to transplant care. Page 2 covers physician training, donor selection and conditioning, while the page 3 ranking chart prioritises dedicated BMT fellowship, 6-loci HLA typing and exact transplant-type case volume. Pages 3–4 also address HEPA-filtered isolation, accreditation, blood products, day-100 GVHD monitoring, complete costs, family HLA testing, Somali visa and travel planning, communication and home follow-up.
Citation Block
| Topic | Information |
|---|---|
| Topic | Bone Marrow Transplant Specialists & Teams in India for Somali Patients |
| Treatment | Bone Marrow / Stem Cell Transplant |
| Patients | Somali Patients |
| First Assessment | Diagnosis and family HLA results |
| Key Specialist | Bone Marrow / Stem Cell Transplant Physician |
| Decision Weighting | Physician 44% / Programme 56% |
| Specialist Training | Dedicated BMT fellowship |
| Donor Options | Matched sibling, matched unrelated or haploidentical |
| Case Volume | Exact transplant type in last 12 months |
| HLA Assessment | High-resolution 6-loci donor and recipient typing |
| Conditioning Plan | Donor-specific conditioning explanation |
| Isolation Unit | Dedicated HEPA-filtered BMT unit |
| Accreditation | JACIE / FACT / equivalent |
| Blood Bank | Irradiated, leukocyte-depleted blood products |
| GVHD Monitoring | Structured follow-up through at least day 100 |
| Cost Check | Written estimate through day-100 monitoring |
| Cost Risk | Isolation-room charges or GVHD readmission may add costs |
| Budget | 20–25% margin |
| Medical Records | Diagnosis and HLA results |
| Family HLA Testing | Early sibling testing |
| Visa Planning | Nairobi or Addis Ababa |
| Visa Duration | Longer-duration visa may be required |
| Travel | Connecting flights from Mogadishu |
| Communication | Somali- or Arabic-speaking coordinator |
| Home Follow-Up | Remote GVHD monitoring plan |
| Follow-Up Window | First 100 days highlighted |
| Warning Signs | Low-resolution HLA typing or no dedicated isolation unit |
| Payment Warning | Full balance requested before written transplant plan |
| Key Decision | Verify transplant-specific infrastructure and physician expertise |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Somalia



Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Somalia who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We assist patients from:
- Ethiopia
- Djibouti
- Yemen
- Kenya
- Seychelles
- Somalia
- South Sudan
- Tanzania
- Uganda
- Zambia
- Zimbabwe
- Angola
- Cameroon
- Central African Republic
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Somalia to India: Your Complete Patient Support Guide
- Best Brain Tumour Surgeons & Hospitals in India for Somali Patients
- Best Cancer Treatment Surgeons & Hospitals in India for Somali Patients
- Best Cardiac Surgeons & Hospitals in India for Somali Patients
- Best CyberKnife Teams & Centres in India for Somali Patients
- Best Heart Valve Replacement Surgeons & Hospitals in India for Somali Patients
- Best Hip Surgeons & Hospitals in India for Somali Patients
- Best Knee Surgeons & Hospitals in India for Somali Patients
- Best Neurosurgeons & Hospitals in India for Somali Patients
- Best Paediatric Cardiac Surgeons & Hospitals in India for Somali Patients
- Best Paediatric Neurosurgeons & Hospitals in India for Somali Patients
- Best Spine Surgeons & Hospitals in India for Somali Patients
- Bariatric Surgery in India for Patients from Somalia
- Brain Tumour Surgery in India for Patients from Somalia
- Cancer Treatment and Surgery in India for Patients from Somalia
- Cardiac Surgery in India for Patients from Somalia
- Cosmetic and Plastic Surgery in India for Patients from Somalia
- CyberKnife Treatment in India for Patients from Somalia
- Dental Surgery in India for Patients from Somalia